Blog

  • Domiciliary Care Business Continuity Plan: A Practical 2026 Guide

    Domiciliary Care Business Continuity Plan: A Practical 2026 Guide

    A domiciliary care business continuity plan explains how your service will protect people and maintain essential care when normal operations are disrupted. It should turn foreseeable risks, such as severe weather, staff shortages, IT failure and supplier disruption, into clear decisions, responsibilities and recovery actions.

    For providers in England, the plan should support safe care, effective governance and reliable service delivery. It must also reflect the realities of care delivered across many people’s homes, not simply copy a generic office continuity template.

    Domiciliary care business continuity plan toolkit with a folder, map, power bank, torch and contact tree
    A visual continuity-planning toolkit with contact, route and backup-power prompts.

    Key takeaways

    • Prioritise essential visits and time-critical support before less urgent activity.
    • Give named roles authority to activate, manage and close the plan.
    • Keep accessible backups for rotas, care records, contact details and escalation routes.
    • Test realistic scenarios and record the learning, actions and owners.
    • Align the plan with contracts, local risks and the service’s actual operating model.

    The short answer

    A strong domiciliary care business continuity plan is a decision system, not a list of possible emergencies. It identifies essential visits, person-specific risks, minimum safe staffing, fallback records, communication routes, decision authority and recovery tests. During disruption, it should help the on-call team answer three questions quickly: who may be harmed, what must continue, and who is authorised to change the normal plan?

    That distinction is important. A generic business plan explains how an organisation intends to operate. A continuity plan explains how safe care will be maintained when normal operations cannot continue.

    Is a business continuity plan required for domiciliary care?

    The Care Quality Commission (CQC) currently identifies a business continuity plan as a supporting document that care homes need to send with a new provider registration application. Its published checklist is still useful for homecare providers because it covers risks, essential services, roles, communication, staffing, IT, testing and recovery. The CQC page does not say that every domiciliary care applicant must submit this document, so providers should not describe it as a universal homecare application requirement.

    Some commissioners require a business continuity plan in home-based care procurements. For example, a 2025 Portsmouth City Council framework notice asked bidders to confirm that they had one in place. Requirements vary by contract, so providers should check each specification. Separately, CQC Regulation 17 requires effective systems to assess, monitor and mitigate risk. Treat continuity planning as an operational control that must work in practice, not as a document created only for a tender or inspection.

    What should a domiciliary care business continuity plan cover?

    On a mobile device, swipe across the table to view all columns.

    Core controls for a domiciliary care continuity plan
    Control areaWhat the plan should answerEvidence to keep
    Essential visitsWhich calls cannot safely be delayed or missed?Priority criteria and reviewed call list
    StaffingHow will shortages, travel disruption or illness be managed?Escalation rota and competence checks
    MedicinesHow will time-critical support continue?Contingency actions linked to care plans
    Records and ITHow will staff access current information if systems fail?Tested backup and recovery record
    CommunicationWho contacts people, families, staff and commissioners?Contact tree and message templates
    SuppliersWhat happens if fuel, personal protective equipment or other essentials are unavailable?Alternatives and supplier contacts
    RecoveryWho decides when normal operations can resume?Recovery checklist and review record

    Use this table as the start of a business impact analysis, not as the finished plan. For each essential activity, record the people affected, the resources it depends on, the longest safe delay, the minimum level of service that can be maintained and the point at which senior escalation is required. The answer will not be identical for every person or every visit.

    Dependencies are easy to overlook. A visit may depend on an available care worker, safe travel, access to current care information, a working telephone, medicines support information and a person being able to answer the door. Map those dependencies together so that the plan does not replace one failed process with another unsafe process. Review the analysis when the service expands, a new branch opens, the care management system changes or the provider accepts a materially different package of care.

    Start with people, not systems

    When reviewing a domiciliary care business continuity plan, the first task is to identify which people could face the greatest harm if support is delayed. A simple priority label is not enough. The service should understand why a visit is time critical, what alternative arrangements exist, who can make a safe decision and how any change will be communicated and recorded.

    This assessment must be based on current care information. Do not assume that a person’s priority remains unchanged after a hospital discharge, medication change, deterioration or change in informal support.

    A domiciliary care business continuity plan should include a short priority decision record that can be used during disruption. It should show the reason a visit is time critical, the likely consequence of delay, the permitted fallback, the person who approved any change and the time of the next review. This keeps decisions person-centred and makes the rationale visible to the next manager taking over.

    Avoid using labels such as red, amber and green without written criteria. Two people with the same colour may face very different risks. One may need time-critical medicines support, whilst another may depend on a visit for nutrition, mobility or safeguarding. The plan should help staff distinguish those needs and decide what can safely change. Where a safe alternative depends on a family member or another professional, confirm that arrangement rather than assuming it will be available.

    Build scenario action cards

    A domiciliary care business continuity plan can become difficult to use during an incident if the operational response is buried in long narrative. Short action cards make the response clearer. Create one card for each material scenario, such as:

    1. Major staff shortage.
    2. Severe weather or travel disruption.
    3. Care management system outage.
    4. Cyber incident or loss of mobile access.
    5. Office or telephone failure.
    6. Fuel shortage or vehicle disruption.
    7. Supplier failure.
    8. Local emergency affecting several people.

    Each card should state the trigger, immediate actions, decision owner, communication route, record to complete and recovery test. It should also explain when senior or external advice is needed. Avoid hard-coding contact details into every page because changes become harder to control. Use a maintained contact schedule with a clear owner and review date.

    Set clear activation thresholds. For example, the on-call manager may need to move from routine rota management to continuity arrangements when several essential visits are at risk or the main system is unavailable beyond an agreed period. A local disruption affecting access to a whole area may also justify activation. Thresholds should prompt judgement, not replace it. A single event involving serious potential harm may justify activation even if a numerical threshold has not been reached.

    In a domiciliary care business continuity plan, each scenario should identify the first 15 minutes, first hour and recovery actions. The first 15 minutes should focus on immediate safety, facts and command. The first hour should confirm priorities, staffing, communications and records. Recovery actions should reconcile missed or changed visits, restore accurate records, confirm outstanding risks and capture learning. This time-based structure makes a plan easier to use when information is incomplete and managers are under pressure.

    Also consider compound disruption. Severe weather may coincide with staff absence, power loss may affect mobile charging, and a cyber incident may disrupt both records and communication. Testing one isolated failure can create false confidence if the service has never considered how dependencies fail together.

    Define roles and decision authority

    The domiciliary care business continuity plan should identify who can activate it, who coordinates care, who manages staffing, who communicates externally and who maintains the incident log. It should also name deputies. A plan that depends on one registered manager being available at all times is fragile.

    Senior oversight matters. The provider or nominated individual should be able to see what happened, which risks were accepted, how people were affected and whether corrective actions were completed.

    Keep the domiciliary care business continuity plan under document control, with a named owner, review date and approved version.

    Use a simple command structure that works out of hours. One person should coordinate the incident, one should maintain the decision log, and operational leads should report confirmed information through an agreed route. The incident lead needs authority to reallocate resources, seek external help and escalate risks. Deputies should have access to the same instructions and records.

    For every important decision, the incident log should record the time, information available, options considered, decision-maker, action owner and review point. This is not paperwork for its own sake. It reduces contradictory instructions, supports handover and allows the provider to examine whether decisions remained proportionate as the situation changed.

    Protect records and communication

    Within a domiciliary care business continuity plan, digital systems improve coordination, but the provider still needs a safe fallback. Decide what minimum information staff need during an outage and how it will remain accurate, secure and accessible. Test whether the fallback works outside normal office hours.

    Paper copies can create their own confidentiality and version-control risks. Any backup process should specify who updates it, where it is stored, how access is controlled and how obsolete copies are destroyed safely.

    Define the minimum information set needed to continue safe care. This may include current visit schedules, key risks, essential care instructions, medicines support information, contact details, access arrangements and escalation routes. Limit the fallback to information staff genuinely need, keep it current and protect it from unauthorised access.

    Test the recovery route, not just the existence of a backup. A file that cannot be opened on the on-call device, a printed rota that is already out of date or a contact list stored in the failed system will not support continuity. The test should confirm access, accuracy, confidentiality and the method for bringing records back together after systems recover.

    Communication templates can save time, but they should leave room for the facts of the incident. State what is known, what is being done, what the recipient needs to do and when the next update will follow. Avoid speculation. Keep a record of messages and unanswered contacts so that communication gaps become visible.

    Test the domiciliary care business continuity plan, then close the learning loop

    A desktop exercise is a practical starting point. Give the team a realistic scenario, such as a six-hour system outage combined with staff absence. Ask them to work through prioritisation, communication, records and recovery. Record delays, unclear decisions and missing information.

    The value comes from the action plan afterwards. Assign each improvement to an owner and deadline, then confirm completion. Keep evidence of the scenario, attendees, decisions, actions and follow-up. This turns testing into governance evidence rather than a tick-box exercise.

    Test the domiciliary care business continuity plan through a varied testing programme. A discussion-based desktop exercise can test decisions and escalation. A call-tree test can check whether staff and key contacts can be reached. A technical recovery test can confirm that essential records are accessible. A live exercise can test a limited operational process without placing people at risk. Choose the method that matches the control being tested.

    Define success before the exercise begins. Useful measures include how quickly essential visits were identified, whether staff used the correct fallback record, whether decision authority was clear, whether communications reached the intended people and whether recovery records were reconciled. Do not mark the test successful simply because the team completed the scenario.

    After the exercise, separate immediate corrections from longer-term improvements. An incorrect telephone number should be corrected at once. A system redesign or contractual issue may need a named project, resources and senior oversight. Review actions until evidence shows they are complete.

    Cabinet Office guidance is written for government departments and arm’s-length bodies, not care providers. Its emphasis on preparation, assurance, recovery and learning is nevertheless useful as general resilience context. Care providers should apply care-sector law, CQC guidance and their contracts first.

    A practical domiciliary care business continuity plan test record

    For each exercise or live incident, retain a short controlled record covering:

    On a mobile device, swipe across the table to view all columns.

    Evidence to retain after an exercise or live incident
    FieldWhat good evidence looks like
    Scenario and assumptionsA realistic disruption with clear boundaries
    People and services affectedCurrent, risk-based impact rather than a generic label
    Decisions madeTime, decision-maker, evidence available and rationale
    CommunicationsWho was told, by whom, when and through which fallback route
    Gaps identifiedMissing information, delay, ambiguity or failed dependency
    Corrective actionNamed owner, deadline, priority and verification method
    Recovery decisionEvidence that normal operation could safely resume

    This record creates an auditable line from planning to testing and improvement. It also prevents a successful exercise from being recorded simply as “completed” when important weaknesses were found.

    Common mistakes

    • Copying a care-home evacuation plan into a homecare service without adapting it.
    • Listing risks without defining operational actions.
    • Treating all visits as identical instead of using person-specific risk.
    • Relying on live cloud systems without a tested fallback.
    • Naming staff but not deputies or decision authority.
    • Running an exercise without completing the resulting actions.
    • Forgetting contract-specific reporting and commissioner contacts.

    A 30-minute manager review

    Ask five questions:

    1. Can we identify our essential visits without the main system?
    2. Can on-call staff access the information needed to make safe decisions?
    3. Do named deputies understand their authority?
    4. Have we tested our highest-risk failure in the last year?
    5. Can we prove that learning from the last test was completed?

    If any answer is uncertain, add it to the service improvement plan rather than assuming the written policy is enough.

    Complete the review with the plan, on-call instructions, current rota, contact schedule and fallback records open together. Sample one high-risk visit and trace what would happen if the main system and usual care worker were unavailable at the same time. Then sample one communication route and one recovery action.

    Record every uncertain answer. Give each action an owner, deadline and verification method. A short evidence-led review is more useful than a long annual meeting that does not test whether the arrangements actually work. Repeat the review after material changes, serious incidents or exercises that expose a weakness.

    How Care Sync Experts can help

    Care Sync Experts can review a provider’s domiciliary care business continuity plan against its service model, policies, governance arrangements and tender commitments. The aim is a usable plan that managers can test, improve and evidence.

    Read our related guides on domiciliary care business planning and preparing for a mock CQC inspection. If you need a structured review of policies, governance and operational evidence, explore our compliance management support.

    Frequently asked questions

    How often should a domiciliary care business continuity plan be tested?

    The testing schedule should reflect the provider’s risks, contractual commitments and changes in the service. Record the rationale, test realistic scenarios and repeat testing after significant changes or when an incident exposes a weakness.

    What is the most important part of the plan?

    The most important part is a workable method for protecting people when essential support is disrupted. That includes current risk information, clear decision authority, communication, records and recovery.

    Can a provider use a generic template?

    A template can provide headings, but the final plan must match the provider’s locations, systems, staffing, people supported, contracts and local risks.

    What records should be available if the care management system fails?

    The provider should define a secure minimum information set for essential care, such as current schedules, key risks, essential instructions, medicines support information, contacts and escalation routes. The fallback must be current, accessible to authorised staff and tested outside normal office hours.


    Sources checked on 7 September 2026

  • CQC Application Stages: What Happens After You Submit?

    CQC Application Stages: What Happens After You Submit?

    Across the CQC application stages, CQC first checks whether the forms and supporting documents meet the minimum requirements after submission. An application that passes those initial checks moves to assessment, which may include questions, interviews and a premises visit. The final outcome is communicated through a formal Notice of Decision or Notice of Proposal.

    The CQC application stages begin with initial checks and continue through assessment to a formal outcome. Submission is the beginning of CQC’s decision process, not the end of your preparation. Keep the proposed service ready, preserve a clean copy of everything sent and make sure the provider, nominated individual and proposed registered manager can explain the same operating model.

    This guide covers new-provider registration in England. It is general information, not a prediction of your application’s timescale or outcome. Always follow the instructions CQC sends about your own application.

    CQC application stages at a glance

    StageWhat CQC is doingWhat the applicant should do
    Receipt and initial checksChecking forms, basic details and required documentsPreserve the exact submission and monitor the authorised inbox
    Rejection at initial checkExplaining why minimum requirements were not metCorrect the full pack, control versions and resubmit as instructed
    AssessmentConsidering fitness and likely complianceKeep evidence current and answer accurately
    Interview or premises activityTesting leadership, capability and readinessPrepare evidence-based explanations, not scripts
    Formal outcomeIssuing a Notice of Decision or Notice of ProposalRead every condition, date and response right carefully

    Stage 1: CQC carries out initial checks

    CQC’s assessment guidance describes two stages: initial checks and assessment. During initial checks, CQC examines whether the forms are complete, basic details are correct and the required supporting documents have been supplied.

    CQC’s current supporting-document guidance says it will reject a new-provider application if required documents are missing or do not meet its document requirements. That makes version control essential.

    Immediately after submission:

    1. save the sent email and attachments in a read-only submission folder;
    2. record the submission date, time, recipient and sender;
    3. calculate a hash or retain a controlled final copy of every file;
    4. monitor the nominated inbox, including spam and quarantine;
    5. make no silent changes to the submitted versions;
    6. keep a separate working folder for later improvements.

    This protects you from answering a question using a different version from the one CQC is assessing.

    Stage 2: CQC confirms or rejects the application at first check

    If the application meets the minimum requirements, CQC sends confirmation after its initial checks. If it does not, CQC says it will email an explanation and the applicant will need to correct or complete the application and submit it again.

    Do not treat a rejected application as permission to patch only the item named in the email. Re-run a complete check. One missing document can hide other inconsistencies, such as a location address that differs from the Statement of Purpose or a staffing plan that does not fit the financial forecast.

    If you resubmit, create a change log showing:

    • the reason given by CQC;
    • every file affected;
    • what changed and why;
    • who approved the revised version;
    • the new submission receipt.

    Stage 3: CQC assesses fitness and likely compliance

    Within the CQC application stages, passing initial checks does not mean registration has been granted. It means the application can proceed to substantive assessment.

    CQC may ask for more information. It assesses whether the applicant and relevant people are fit and whether the proposed systems are likely to support compliance with the Health and Social Care Act 2008 and associated regulations. The focus is not simply whether documents exist. CQC considers whether the proposed service can be safe, effective, caring, responsive and well-led.

    Keep the following current during this period:

    • the Statement of Purpose;
    • business plan and financial forecast where required;
    • staffing structure and recruitment progress;
    • policies and operational procedures;
    • premises and location evidence;
    • DBS and fitness evidence;
    • training and competence plans;
    • governance, audit and escalation arrangements.

    If something material changes, do not hide it or improvise. Check the correct notification or application route and obtain advice where needed.

    Stage 4: CQC may interview key people

    CQC says it may interview the applicant and registered manager by telephone, online or face to face. The precise participants depend on the legal entity and application.

    Interview preparation should test whether leaders understand their responsibilities and their own service. It should not teach memorised slogans.

    Be ready to explain:

    • what regulated activity you are applying for and why;
    • who will receive the service and what needs the model is designed to meet;
    • how the service will recruit, deploy and supervise competent staff;
    • how safeguarding, medicines, incidents and complaints will be managed;
    • how leaders will monitor quality and act on risk;
    • how the financial and staffing assumptions support safe delivery;
    • how the provider, nominated individual and registered manager roles differ;
    • what will happen if the service grows or a key assumption changes.

    Every answer should agree with the submitted pack. If the evidence has changed since submission, identify the change openly and explain the control around it.

    Stage 5: CQC may visit the premises

    CQC says it will need to visit the premises for most new registrations and some changes. A premises visit may help it verify that the proposed location is real, suitable and ready for the regulated activity.

    For a domiciliary care or supported living office, be able to show how care will be planned and co-ordinated, how staff will be managed, how confidential information will be protected and how CQC can access the location. Our live CQC registration guide for domiciliary care explains the wider application and office-readiness context.

    Do not create a staged office that does not reflect your intended operating model. The physical environment, documents and leadership explanation should align.

    Stage 6: CQC reaches a formal outcome

    For the final CQC application stages, CQC’s outcome guidance identifies two assessment outcomes.

    Notice of Decision

    CQC may decide to grant registration, including any agreed conditions. Read the notice and certificate carefully. Confirm the legal entity, regulated activities, locations and conditions before carrying on regulated activity.

    Notice of Proposal

    CQC may propose to refuse registration or grant it with conditions that differ from those requested. CQC says an applicant has 28 calendar days to make written representations against a Notice of Proposal.

    This is a formal legal stage. Record the date received, calculate the deadline carefully and obtain appropriate advice. Do not rely on an informal conversation to protect a statutory response right.

    How long does CQC registration take after submission?

    CQC’s assessment guidance says the CQC application stages are rigorous and can take several months. It does not promise one fixed timescale for every application. Complexity, completeness, queries, interviews, premises activity and CQC workload can all affect progress.

    Avoid publishing or planning around an invented approval date. Build a cash-flow and mobilisation plan that can tolerate uncertainty, and do not provide regulated activity until the registration and relevant conditions legally permit it.

    A practical readiness rhythm between CQC application stages

    Weekly

    • monitor the authorised application inbox;
    • record CQC correspondence and deadlines;
    • confirm that key people remain available;
    • log material changes or emerging risks.

    Fortnightly

    • check that policies, premises and recruitment evidence still reflect reality;
    • reconcile application statements with the current operating plan;
    • review readiness actions and overdue decisions.

    Before every CQC response

    • verify the request and deadline;
    • retrieve the exact submitted version;
    • answer the question asked;
    • separate facts, evidence and plans;
    • have a second person check accuracy and consistency;
    • preserve the sent response and receipt.

    Common mistakes after submission

    Assuming silence means approval

    Only a formal decision establishes the outcome. Keep monitoring and preparing.

    Changing the business model without checking impact

    A new location, legal entity, target group, regulated activity or leadership arrangement may affect the application. Get the route right before acting.

    Sending inconsistent follow-up evidence

    Later answers become part of the assessment trail. Compare them with the original pack before sending.

    Preparing leaders with generic model answers

    CQC needs to assess the people and proposed service, not a rehearsed script. Use scenario questions and evidence retrieval.

    Treating initial acceptance as registration

    Passing minimum checks only allows the application to move into assessment. It is not permission to carry on regulated activity.

    Watch: avoiding rejection under the 2026 application rules

    Care Sync Experts’ video, New CQC Rules February 2026: No Second Chances on Your Application, explains why completeness and consistency need attention before and after submission. Use CQC’s latest supporting-document guidance as the controlling source.

    How Care Sync Experts can help

    Care Sync Experts can help you maintain an auditable post-submission file, prepare key people for evidence-based interviews and test whether follow-up responses remain consistent with the application.

    Explore our CQC registration support or book a consultation for a controlled application-readiness review.

    For the preparation stage, use our CQC application guide for 2026 and make sure any interview preparation remains grounded in the evidence actually submitted.

    Frequently asked questions

    Does CQC acknowledge a registration application?

    CQC says it sends a confirmation email after completing initial checks if the application meets the minimum requirements for assessment. This confirmation records progress through the first of the CQC application stages, but it is not registration.

    What happens if documents are missing?

    CQC says it will reject an application that does not include all required documents or where the documents do not meet its requirements. The applicant must correct or complete the pack and submit again.

    How long do the CQC application stages take?

    CQC says registration is rigorous and can take several months, but it does not promise one fixed duration for every application. Completeness, complexity, requests for information, interviews, premises activity and the circumstances of the application can affect progress. Plan for uncertainty and rely on CQC’s correspondence about your own application.

    Will CQC interview the registered manager?

    CQC may interview the applicant and registered manager by telephone, online or face to face. The activity depends on the application and assessment.

    Does CQC visit the office before registration?

    CQC says it needs to visit premises for most new registrations and some changes. Keep the proposed location operationally credible and ready for verification.

    Can I start delivering regulated care once the application passes initial checks?

    No. Initial acceptance is not registration. Carrying on a regulated activity without the required registration can be an offence. Wait for the formal decision and check every condition.

    What can I do after a Notice of Proposal?

    CQC says you can make written representations within 28 calendar days of receiving the notice. This is a formal stage, so record the deadline and obtain appropriate advice promptly.

    Official source check completed 8 September 2026. Check the latest CQC assessment, supporting-document and outcome guidance, and follow the correspondence for your own application.

  • CQC First Assessment: Essential 2026 Guide for Unrated Care Providers

    CQC First Assessment: Essential 2026 Guide for Unrated Care Providers

    If your adult social care service has been registered for more than a year but has not had a CQC first assessment, treat the wait as an active evidence-management period. CQC’s 2026 priorities include services registered for over a year that have not yet been assessed. That increases relevance, but it does not give any provider a guaranteed inspection date.

    The safest response is to keep your registration details, provider information return, risk controls, care evidence, workforce records and improvement actions current every month. Do not create a last-minute paperwork exercise. Build a clear trail that shows what your service does, how leaders know it is working and what changes when evidence identifies a gap.

    What the CQC first assessment priority means

    CQC’s May 2026 assessment priority update says adult social care activity is focused on urgent and emerging risks, services that have never been assessed where CQC data indicates very high risk, other services flagged as very high risk and services registered for over a year that have not yet been assessed. Its official adult social care provider bulletin describes this as a balanced approach across priority areas.

    For an unrated provider, the practical meaning is straightforward. Your service may now sit within a named priority group, so leaders should be able to retrieve current evidence without a scramble. The priority is not a verdict about quality. It does not mean that CQC has identified a concern simply because a service remains unrated.

    The priority also sits alongside CQC’s wider work to change its assessment approach. Our CQC assessment changes 2026 guide explains the separate methodology pilots and why providers should continue following current published guidance until the regulator confirms and implements a new approach. This article owns a different question: how an unassessed provider can keep CQC first assessment evidence ready now.

    What the priority does not mean

    Unsafe assumptionSafer interpretationProvider action
    CQC will visit immediately after the first anniversaryThe service is within a named priority group, but CQC balances several priorities and retains flexibilityKeep evidence current without predicting a date
    Unrated means compliantNo rating is not evidence that all standards are metUse audits, feedback and oversight to test practice
    Unrated means CQC has concernsThe absence of a rating does not establish a quality findingSeparate known facts from assumptions
    A large policy folder proves readinessCQC assesses quality and performance using evidence from several categoriesConnect documents to practice, outcomes and improvement
    Preparation should start only after contactCore records should be controlled as part of normal governanceRun a recurring readiness cycle

    A good CQC first assessment plan is deliberately date-neutral. It helps the service today, whether CQC contacts the provider next week or later. It also avoids anxiety-driven decisions such as generating duplicate records, rewriting stable policies without evidence or coaching staff to recite slogans.

    Build a CQC first assessment evidence map

    CQC’s current provider assessment guidance organises evidence across categories and retains the five key questions: safe, effective, caring, responsive and well-led. A provider does not need a separate copy of every record under every heading. It needs an index that points to the live source, names the owner, shows the review date and records what happened after a finding.

    CQC first assessment evidence map for adult social care providers

    1. People, care and outcomes

    Sample care plans, risk assessments, reviews and daily records. Check whether they reflect current needs, preferences, communication requirements and consent decisions. Pair records with feedback, complaints, compliments and evidence of changes made. The aim is not volume. It is a credible connection between what the service planned, what staff delivered and what people experienced.

    2. Safety and risk control

    Review incidents, safeguarding, medicines, infection prevention, staffing risks and business continuity. For each significant issue, show the immediate response, investigation, learning, accountable action and follow-up check. An action marked complete without a test of impact is weaker than a smaller record that shows the risk reduced.

    3. Workforce competence

    Check recruitment, induction, mandatory and role-specific learning, supervision, appraisal and observed practice. Training attendance alone does not demonstrate competence. Managers should be able to explain which tasks require direct observation, how concerns are escalated and what evidence supports a decision that a worker can practise safely.

    4. Governance and improvement

    Bring together audits, meeting minutes, performance measures, complaints themes, incident trends and improvement plans. Assign an owner and deadline to every open action. Then test whether the action changed practice or outcomes. Care Sync’s compliance management support for care providers can help leaders connect policies, audits, actions and inspection readiness into one controlled system.

    5. Regulatory control

    Confirm that registration details, regulated activities, conditions, registered manager information and statement of purpose remain accurate. Check that required notifications were made through the correct route and retained with the supporting decision record. Review the annual provider information return process rather than waiting for its deadline.

    Use a 30-day CQC first assessment readiness cycle

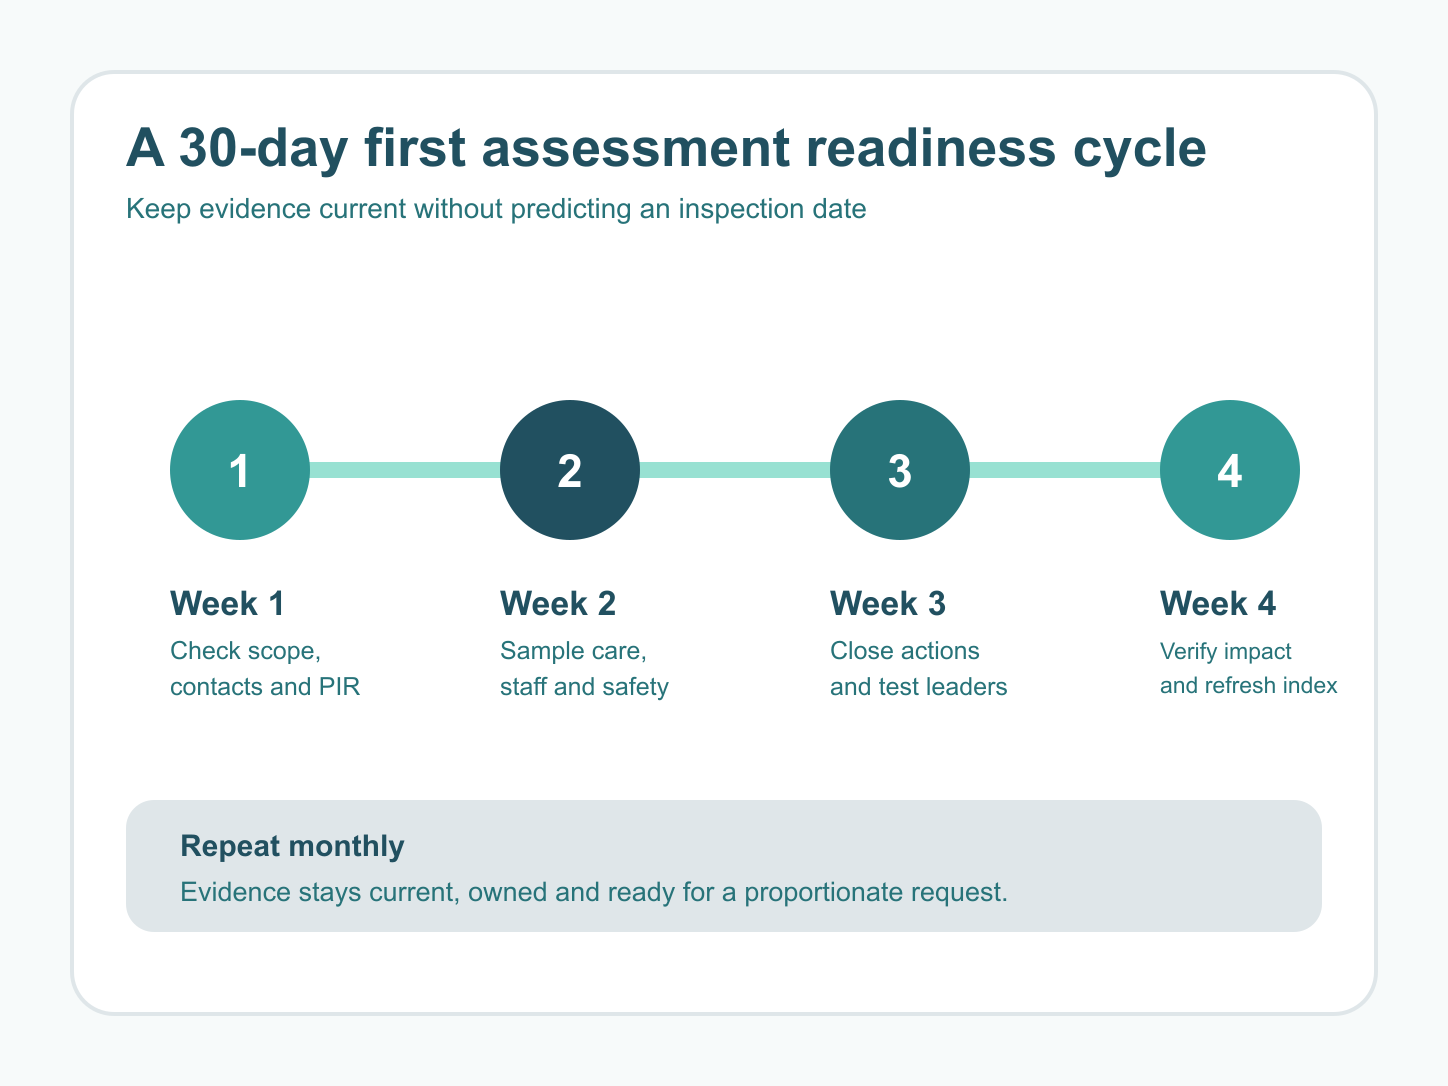
    A monthly cycle keeps preparation proportionate. It does not need to repeat a full mock inspection. Each week should have one focused management task, a named owner and a short record of findings.

    Thirty-day first CQC assessment readiness cycle for an unrated care provider
    1. Week 1, confirm regulatory scope. Check registration details, contacts, regulated activities, statement of purpose, notifications and the PIR calendar.
    2. Week 2, sample operational evidence. Review a balanced selection of care, risk, medicines, staffing, complaints and feedback records.
    3. Week 3, close and test actions. Challenge overdue actions, verify completed work and escalate any safety concern through the correct process.
    4. Week 4, test leadership explanations. Ask managers what the service’s main risks are, what evidence supports that view and what improved during the month.

    Record the sample, findings, decisions, owners and next review date. Rotate the detail so the cycle covers the whole service over time. A small domiciliary care service and a larger multi-location provider may use different sample sizes, but both need a method that is proportionate and repeatable.

    Prepare registered managers and leaders for evidence conversations

    CQC first assessment readiness is not about memorising model answers. Leaders should understand the service well enough to explain current strengths, risks and improvement work in plain language. Their account should agree with frontline practice and records.

    • What are the three most important current risks, and how do you know?
    • What changed after the most recent incident, complaint or safeguarding concern?
    • How are people and relatives involved in decisions and improvement?
    • Which workforce competence gap needs the closest oversight?
    • Which audit action is overdue, who owns it and what is the risk?
    • How do you know that a completed action improved care?

    Use these questions in normal governance meetings. If answers rely on general statements such as staff know what to do or policies are up to date, ask for the evidence behind them. A CQC mock inspection can help test the connection between leadership accounts, staff practice and records, but it cannot guarantee the timing or outcome of a real assessment.

    Common CQC first assessment preparation mistakes

    Waiting for a visit date

    A provider can lose months of useful improvement time by treating CQC first assessment readiness as an event. Keep the evidence index, risk picture and action plan current as part of everyday governance.

    Creating evidence after the fact

    Do not reconstruct meetings, checks or decisions that did not happen. Record gaps truthfully, take proportionate action and retain the follow-up evidence. A transparent improvement trail is safer than a polished but unreliable record.

    Ignoring the PIR until the deadline

    CQC’s adult social care PIR guidance says registered managers receive an annual request and a four-week deadline. Build the underlying evidence throughout the year so the return reflects current practice and outcomes.

    Confusing legal standards with an assessment framework

    The CQC Fundamental Standards are legal minimum requirements. Assessment questions and evidence categories help CQC judge quality. Providers need to understand both, but should not present draft methodology changes as current law.

    Overloading staff with inspection scripts

    Staff should know how to deliver care safely, find current information, raise concerns and explain their role. Rehearsed phrases are not a substitute for competence. Use supervision, observation and team discussion to build genuine understanding.

    What to do when CQC contacts your service

    1. Verify the request. Confirm the sender, location, deadline, scope and secure submission route.
    2. Name one coordinator. Keep a request log so evidence, owners and deadlines are visible.
    3. Use existing records. Provide the information requested, not a new volume of documents created for appearance.
    4. Check accuracy and confidentiality. Make sure the material relates to the correct service and only includes necessary personal information.
    5. Disclose genuine gaps. Explain immediate safeguards, corrective action, ownership and follow-up.
    6. Keep a submission receipt. Record what was sent, when, by whom and through which authorised route.

    Current CQC guidance indicates that providers do not need to send assessment evidence proactively unless it is requested. Keep evidence ready, but use the regulator’s specified channel and timetable when a request arrives.

    How Care Sync Experts can help

    Care Sync Experts can help an unrated provider review its evidence map, governance controls, policy alignment and mock assessment readiness. The purpose is to identify real gaps, assign proportionate actions and build a reliable operating system for compliance.

    If your service has been registered for more than a year and you want an independent readiness review, book a consultation with Care Sync Experts.

    Frequently asked questions

    When will CQC carry out a first assessment after registration?

    There is no fixed CQC first assessment date published for every adult social care service. CQC’s 2026 priorities include services registered for over a year without an assessment, alongside risk-led priorities. Keep evidence current without assuming a guaranteed timetable.

    Does being registered for more than a year guarantee an immediate CQC assessment?

    No. It places the service within a named priority group, but CQC describes a balanced approach and retains flexibility to respond to urgent risks and exceptional circumstances.

    Should an unrated provider send evidence to CQC before it is requested?

    Keep the evidence organised and current, but do not submit it proactively unless CQC asks or a separate statutory process requires it. Follow the instructions, scope and secure route in any request.

    What evidence should an unrated care provider keep ready?

    Maintain current evidence on people’s care and outcomes, safety and risk, workforce competence, governance and improvement, and regulatory control. Each source should have an owner, review date, finding and follow-up where relevant.

    Does an unrated service still need to complete a PIR?

    Yes. CQC says adult social care services submit a provider information return each year. Registered managers receive the request and should complete it with the latest service information by the stated deadline.

    Can a mock inspection guarantee the outcome of the first CQC assessment?

    No. A mock inspection can identify gaps and test whether records match practice, but it cannot control CQC’s timing, evidence collection or judgement. Treat it as an improvement tool, not a promise.

    Official source check completed 5 August 2026. Review the latest CQC assessment priority update, provider assessment guidance and adult social care PIR guidance before changing your compliance process.

  • CQC Regulation 9A After the 2026 Review: A Practical Visiting Policy Guide for Care Home Providers

    CQC Regulation 9A After the 2026 Review: A Practical Visiting Policy Guide for Care Home Providers

    CQC Regulation 9A requires relevant care home, hospital and hospice providers in England to facilitate visits unless exceptional circumstances make this unsafe. For care home providers, a visiting policy should begin with the resident’s wishes, avoid blanket restrictions, use individual risk assessment and record how any restriction will be reviewed and removed.

    The Department of Health and Social Care reviewed CQC Regulation 9A in 2026 and confirmed that the standard remains in force. Its review found that the regulation had clarified expectations, but that awareness, decision making, communication and monitoring were still inconsistent. This guide turns the current Care Quality Commission guidance on Regulation 9A and the 2026 government review into a practical policy and evidence check for care home leaders.

    Key takeaways

    • CQC Regulation 9A applies to relevant regulated activities in care homes, hospitals and hospices in England.
    • Residents should be supported to receive visits and should not be discouraged from visits out, unless exceptional circumstances apply.
    • Restrictions should be individual, necessary, proportionate, documented and time-limited.
    • The resident, and where appropriate family, friends or advocates, should be involved in decisions.
    • Policies should explain consent, mental capacity, complaints, communication and review arrangements.

    What does CQC Regulation 9A require?

    CQC Regulation 9A creates a fundamental standard for visiting and accompanying in relevant care homes, hospitals and hospices. Unless exceptional circumstances apply, providers must facilitate visits, must not discourage care home residents from taking visits out and must enable people attending certain hospital or hospice appointments to be accompanied.

    For a care home, the practical starting point is open, person-centred visiting. CQC guidance says providers should support people to receive visits from those they want to see, when they want to see them, unless exceptional circumstances prevent this. Individual risk assessment matters because the person’s needs, preferences, environment and the nature of the risk may differ.

    CQC Regulation 9A does not require a person to receive a visit against their wishes. Where the person lacks capacity for the relevant decision, the provider must work within the Mental Capacity Act 2005 and the best interests framework. The person’s wishes remain central, and a visitor’s preference does not override a capacitous resident’s decision.

    Which services are within the scope of CQC Regulation 9A?

    CQC Regulation 9A applies to a registered person carrying on a relevant regulated activity in a care home, hospital or hospice. It does not apply to every adult social care setting. The government review states that supported living and extra care housing are outside its scope because the accommodation and visiting arrangements in those settings are not regulated by CQC in the same way.

    Setting or situationCQC Regulation 9A positionProvider action
    CQC-regulated care home carrying on a relevant regulated activityWithin scopeAudit visiting, visits out and restriction decisions against CQC Regulation 9A
    Hospital or hospice within the defined scopeWithin scopeCheck visiting and accompaniment arrangements
    Supported living or extra care housingOutside CQC Regulation 9A scopeRespect the person’s home, tenancy and existing legal rights, and do not present CQC Regulation 9A as the governing rule
    Person does not consent to a visitNo duty to force a visitRecord and respect the person’s decision

    This scope check prevents a common governance mistake: applying a care home policy to a person’s own home in supported living. Care Sync’s broader guide to the CQC fundamental standards can help leaders place CQC Regulation 9A alongside other provider duties without blurring service types.

    A practical CQC Regulation 9A visiting policy audit

    A strong CQC Regulation 9A visiting policy should explain how the service enables contact in ordinary circumstances and how it makes fair decisions when risk changes. It should not begin with a list of bans. The policy needs enough detail to guide staff, but the actual decision must still respond to the individual resident and the evidence available at that time.

    Policy controlWhat to checkEvidence to retain
    Resident preferencesHow visiting wishes, important relationships and visits out are discussedCare plan or preference record, reviewed with the person
    Open visiting arrangementsWhether ordinary access is easy to understand and arrangePublic information, welcome material and staff briefing
    Individual risk assessmentWhether the specific person, visitor, setting and risk are consideredDated assessment, precautions and decision rationale
    Consent and capacityHow the person’s decision and lawful authority are establishedConsent record or decision-specific capacity and best interests record where required
    AlternativesWhat safer options are offered if the preferred arrangement cannot proceedOptions discussed and the person’s response
    Review and removalWho reviews a restriction, when and against what evidenceNamed owner, review date and closure decision
    Complaints and challengeHow residents and visitors can raise concerns without fearAccessible route, response record and governance learning

    How should CQC Regulation 9A exceptional circumstances be recorded?

    CQC describes exceptional circumstances as a situation where, despite precautions, the visit or accompaniment would still pose a serious risk to the health, safety or welfare of the person or others on the premises. This is a high threshold. A general concern, staff preference or operational inconvenience is not enough on its own.

    CQC Regulation 9A six-control visiting decision record for care home providers

    Use a decision record that answers six questions: What does the person want? What is the specific serious risk? Which precautions were considered or tried? Who was involved and who had authority to decide? What alternatives and communication were offered? When will the restriction be reviewed and removed?

    The record should separate facts, professional judgement and the person’s account. It should also show why a less restrictive option would not manage the risk. If circumstances change, the restriction should change too. CQC guidance says providers should remove the restriction and allow visiting again as soon as the exceptional circumstances no longer apply.

    CQC Regulation 9A communication, staff practice and complaints

    A policy does not work if only senior managers know it. Staff who answer the telephone, welcome visitors, plan care, lead shifts and respond to concerns need a shared understanding of the ordinary visiting position, the exceptional circumstances threshold and the escalation route.

    1. Explain the normal position. Tell residents and visitors how the service supports contact and visits out.
    2. Communicate any restriction personally. Give the reason, precautions considered, alternatives, review date and named contact.
    3. Provide an accessible challenge route. Explain the complaints process and how advocacy support can be used.
    4. Brief staff consistently. Avoid different explanations from different shifts.
    5. Review themes. Use complaints, compliments, incidents and visiting records to identify policy or training gaps.

    The 2026 government review reported concerns about unclear decision making, variable communication and obstacles to raising complaints. Providers should therefore test whether their process feels usable from the resident’s and visitor’s perspective, not only whether a policy document exists.

    What changed after the 2026 review of CQC Regulation 9A?

    The review did not remove or replace CQC Regulation 9A. It found that the standard had reinforced the importance of visiting and prompted providers to review practice, but that implementation remained uneven. The government said it would develop clearer communications, awareness resources and a public-facing decision process, improve the clarity of Capacity Tracker visiting questions and continue to monitor the position.

    Care home providers should treat this as a prompt to improve evidence and consistency now. Do not wait for a future resource before correcting a blanket restriction, an unclear complaints route or a decision record with no review date. At the same time, do not describe proposed future legislation as if it is already in force. The government’s March 2026 announcement on stronger visiting rights says further legislative changes are being explored.

    The Capacity Tracker questions are useful monitoring information, but they are not a complete CQC Regulation 9A compliance test. A yes or no return cannot replace individual care planning, risk assessment, consent, communication, complaints handling and documented review.

    A first 30 days action plan for care home providers

    Days 1 to 7: check scope and policy wording

    Confirm which locations and regulated activities are within CQC Regulation 9A scope. Review the policy for blanket rules, vague exceptional circumstances wording and incorrect references to supported living. Check that visits into the home and visits out are both covered.

    Days 8 to 14: sample recent decisions

    Take a small, representative sample of visiting restrictions or altered arrangements. Check the person’s wishes, the risk described, precautions considered, involvement, alternatives, communication and review. Record gaps without assuming why they occurred.

    Days 15 to 21: brief staff and test communication

    Use anonymised scenarios to test staff understanding. Ask how they would respond to a resident who wants a visit, a relative challenging a restriction or an infection-control concern. Check that staff know who can authorise a restriction and how to escalate uncertainty.

    Days 22 to 30: close actions and set governance

    Assign owners and deadlines for policy, training or record changes. Add CQC Regulation 9A to the appropriate governance review. Track restrictions that remain open and require evidence at the next review rather than carrying them forward automatically.

    What evidence should managers sample during a visiting policy audit?

    A policy review should test real practice as well as the wording on the page. Select a small range of recent visiting decisions, including ordinary visits, visits that needed adjustments and any arrangement that was restricted. The aim is to see whether the service moved from the resident’s wishes to an evidence-based decision, communicated it clearly and reviewed it at the right time. Do not assume that an incomplete record proves poor intent, but treat the missing evidence as a governance gap that needs an owner and a deadline.

    Sample the full decision journey

    For each sampled record, check whether the file tells a coherent story. A reviewer who was not involved should be able to understand what the person wanted, what risk was identified, which precautions were considered, who took part in the decision and what happened next. Look across care records, risk assessments, daily notes, communication logs, complaints records and governance minutes where these are relevant. One document does not need to hold every detail, but the evidence should connect without contradiction.

    • Resident’s wishes: record the person’s preference, including the timing, frequency and people important to them.
    • Decision authority: identify who made the decision and the basis on which they were authorised to do so.
    • Specific risk: describe the actual health, safety or welfare concern rather than relying on a general label.
    • Precautions considered: show which less restrictive options were discussed, tried or ruled out, with reasons.
    • Communication: record what was explained, to whom, in what format and how questions or disagreement were handled.
    • Review and closure: give the next review date, the evidence needed and the point at which the restriction ended.

    Test whether the restriction can end

    The strongest review question is not simply whether the original decision was reasonable. Ask whether the evidence still supports it today. Check for updated health information, changes in the environment, the effect of precautions and the resident’s current wishes. Where the risk has reduced, the visiting arrangement should be reconsidered promptly. If a restriction remains, the record should explain why, identify the next review and avoid repeating the previous wording without fresh analysis.

    How should infection prevention and safeguarding concerns be handled?

    Infection prevention and safeguarding may create genuine visiting concerns, but neither should become an automatic reason for a blanket ban. Start with the particular person, visitor, setting and risk. Separate what is known from what is suspected, obtain appropriate professional advice where needed and consider precautions that preserve contact. The service should also recognise that isolation, loss of family contact and disrupted advocacy can create risks of their own.

    Use precautions before restriction

    • Consider a different room, route, time or format for the visit.
    • Use proportionate hygiene, ventilation or protective measures where the assessed risk requires them.
    • Agree supervision or staff support where there is a specific safeguarding concern.
    • Offer remote or alternative contact as an additional option, not an automatic substitute for an in-person visit.
    • Review whether the precaution remains necessary and remove it when the evidence no longer supports it.

    The record should explain why the chosen measure is the least restrictive workable response. If the preferred visit cannot proceed, staff should discuss alternatives with the resident and relevant people rather than presenting a fixed decision. Any safeguarding action should follow the service’s safeguarding process, whilst the visiting decision record remains clear about the person’s wishes, the evidence considered and the review route.

    Keep roles and escalation clear

    Frontline staff should know who can approve a restriction, who can obtain clinical or safeguarding advice and who must review an urgent decision made outside normal management hours. The registered manager should be able to identify open restrictions, overdue reviews and repeated themes. Where staff disagree or evidence is uncertain, the escalation route should encourage a timely review rather than leaving an informal restriction in place.

    A simple governance dashboard for visiting decisions

    A monthly governance check can help a provider see whether CQC Regulation 9A is working in practice. Use a small set of measures that prompt action, not a league table that rewards low reporting. Review the number of current restrictions, how many are overdue, whether residents and relevant visitors were involved, the use of alternatives, complaints or concerns and whether repeated issues point to a policy, staffing or communication weakness.

    Governance questionEvidence to reviewAction trigger
    Are any visiting restrictions still open?Restriction log and individual recordsConfirm owner, rationale and next review
    Are reviews completed when due?Review dates and meeting recordsEscalate overdue decisions immediately
    Were people involved and informed?Care notes and communication recordsCorrect gaps and provide accessible information
    Are themes recurring?Complaints, incidents, safeguarding and audit findingsUpdate policy, training or oversight controls

    Record the action, responsible person, deadline and follow-up test for every material gap. At the next governance review, check whether the change improved practice. This closes the loop between policy, individual decisions and sustained oversight, whilst keeping the resident’s rights and experience at the centre.

    How Care Sync Experts can help

    Care Sync Experts can help care providers review CQC Regulation 9A visiting policies, decision records, staff guidance and governance evidence against current CQC expectations. Our compliance management support can help turn regulatory guidance into workable controls that fit the service.

    If you want practical support with a CQC Regulation 9A policy audit or wider compliance review, book a consultation with Care Sync Experts.

    Frequently asked questions

    Does CQC Regulation 9A allow a care home to stop all visits?

    Only exceptional circumstances under CQC Regulation 9A may justify a restriction, and the provider should still consider necessary and proportionate precautions. A blanket rule should not replace individual assessment. Record the serious risk, the person’s wishes, precautions, alternatives, decision authority and review date.

    What counts as exceptional circumstances under CQC Regulation 9A?

    CQC describes exceptional circumstances as a situation where, despite precautions, visiting or accompaniment would still pose a serious risk to health, safety or welfare. The decision should be evidence-led, individual and reviewed when circumstances change.

    Does CQC Regulation 9A apply to supported living?

    No. The government review states that supported living and extra care housing are outside CQC Regulation 9A because CQC does not regulate the accommodation and visiting arrangements in those settings in the same way. Providers must still respect the person’s home and applicable rights.

    Should a care home review its CQC Regulation 9A visiting policy after the 2026 review?

    Yes. The review identified inconsistent awareness, decision making and communication. A provider should check that its policy supports open visiting, individual risk assessment, consent, clear communication, complaints and time-limited review without presenting future government proposals as current law.

    Is the Capacity Tracker visiting return enough to show compliance?

    No. Capacity Tracker information can support monitoring, but it does not replace the CQC Regulation 9A evidence needed for individual visiting preferences, risk decisions, precautions, involvement, communication, complaints and review. The 2026 government review said the visiting questions and completion instructions would be clarified.

    Official source check completed 9 August 2026. Check the latest CQC Regulation 9A guidance and government review before changing a CQC Regulation 9A policy or restriction control. This article provides general compliance information, not legal advice.

  • Adult Social Care Winter Planning 2026/27: 9 Actions Before September

    Adult Social Care Winter Planning 2026/27: 9 Actions Before September

    Adult social care winter planning should start now, before local systems complete their draft plans at the end of August. Independent providers are not automatically responsible for NHS board assurance, but they should be ready to explain their capacity, continuity arrangements and escalation routes to commissioners and system partners.

    The practical priority is a short, tested plan that protects continuity of care when staffing, transport, energy, infection and discharge pressures rise together. This guide turns current official expectations into nine provider actions for England, without presenting NHS duties as direct legal duties for independent care providers.

    Why adult social care winter planning matters in August 2026

    NHS England’s winter planning 2026/27 letter, published on 17 July 2026, says every local area should complete a joint draft winter plan by the end of August. Those plans should involve NHS services, local authorities, social care and the third sector. The letter places formal planning and assurance responsibilities on integrated care boards and NHS providers.

    For an independent care provider, the decision is different. You need to understand how your service will contribute, what information partners may need and which local pressures could affect safe delivery. Do not assume that the NHS board assurance deadline applies directly to your organisation unless a commissioner or contract says so.

    UKHSA guidance for adult social care managers gives providers a more direct operational benchmark. It says organisations should plan throughout the year, agree cold-weather arrangements and distribute them to managers and frontline staff before 1 November.

    The 9-action adult social care winter planning matrix

    Readiness areaProvider action before SeptemberEvidence to retainOwner question
    System partnershipConfirm the local commissioner, discharge and escalation contacts.Contact list, meeting note and agreed reporting route.Who speaks for the service?
    CapacityModel normal, surge and extreme pressure scenarios.Capacity assumptions, exclusions and review trigger.What can we safely offer?
    DischargeDefine information and resources needed before accepting a placement or restart.Admission checklist and escalation record.What would make acceptance unsafe?
    Infection preventionRefresh outbreak, respiratory infection and staff sickness arrangements.Current procedures, stock check and briefing record.Can we act quickly?
    People at higher riskIdentify people who may need additional monitoring or support during cold weather.Person-centred review and lawful alert method.Who needs a different response?
    WorkforceTest rotas against sickness, travel disruption and seasonal demand.Contingency rota, skills matrix and agency controls.Which shift is most fragile?
    Transport and suppliesMap alternative routes and critical suppliers.Supplier contacts, minimum stocks and delivery fallback.What stops care reaching people?
    Utilities and premisesPlan for heating, power, water and communication disruption.Maintenance evidence, emergency contacts and equipment checks.How long can we operate?
    Escalation and testingRun a short scenario exercise and record actions.Exercise note, action log, owner and due date.Did the plan work?

    This matrix is a Care Sync implementation aid, not an official government template. It helps a provider turn broad adult social care winter planning into evidence that managers can use, test and improve.

    Adult social care winter planning cycle covering continuity, staffing, transport, utilities and infection prevention

    1. Confirm who owns the local conversation

    Start adult social care winter planning by naming one senior winter lead for your service. This does not mean copying the NHS assurance structure. It means avoiding fragmented messages when commissioners, local authorities, primary care teams or discharge teams ask about capacity and risks.

    Ask your commissioner when the local winter planning conversation will happen, which provider forums are involved and how capacity changes should be reported. Record the answer, the contact and the date. If no route is offered, keep evidence that you asked and continue with your internal plan.

    2. Model three realistic capacity scenarios

    Adult social care winter planning is stronger when capacity is expressed with assumptions. A care home may model occupied beds, vacancies, isolation constraints and staffing ratios. A domiciliary care provider may model available care hours, travel time, double-handed calls and geographical limits.

    • Normal: expected demand with planned staffing and routine absence.
    • Surge: higher demand, delayed discharge or increased sickness that can be managed with agreed controls.
    • Extreme pressure: conditions in which accepting more work could threaten safe delivery.

    State what changes between scenarios, what remains fixed and who approves movement from one level to another. This prevents an optimistic capacity figure being treated as an unconditional promise.

    3. Make discharge readiness explicit

    For adult social care winter planning, NHS England expects local systems to plan social care and intermediate care capacity jointly, support discharge and reduce hospital occupancy ahead of Christmas. An independent provider can contribute by making acceptance criteria clear.

    Review the information, equipment, medication arrangements, staffing competence and environmental checks required before a new placement, hospital discharge or restart of home care. Record who can make the decision out of hours. A faster response is useful only when the provider can still deliver safe, person-centred care.

    4. Refresh infection prevention arrangements

    Adult social care winter planning should include a review of outbreak reporting, acute respiratory infection guidance, staff sickness escalation, cleaning supplies and communication with visiting professionals. The adult social care winter letter for 2025/26 told councils and providers to maintain business continuity plans and continue following infection prevention and control guidance. It is historical context for the previous winter, not a new 2026/27 instruction.

    Keep the winter plan aligned with current public-health guidance, your service risk assessment and any commissioner instructions. Avoid adding blanket restrictions that are not supported by the current situation or guidance.

    5. Identify people who may need additional support

    Person-centred adult social care winter planning follows UKHSA advice to identify people at higher risk from cold weather and establish ways to alert and monitor them. In home care, this may include planned checks on room temperature, food, medicines and heating concerns. In residential settings, it includes reliable heating, safe access and appropriate monitoring arrangements.

    Use person-centred information and lawful data sharing. Do not create a broad list based only on age or diagnosis. Record why extra support is relevant to the person, what staff should observe, what action is expected and who should be contacted.

    6. Test workforce resilience, not just headcount

    Workforce-focused adult social care winter planning looks beyond headcount because a rota can appear fully staffed while remaining fragile. Check travel dependencies, key-holder coverage, medication competence, on-call leadership, lone-working risks and the effect of simultaneous sickness. Consider how holiday periods affect agency availability and management oversight.

    Set clear thresholds for escalating shortages. Brief staff on what they must report and how priorities will be decided if normal delivery is disrupted. Link the plan to supervision, competence and workforce records, rather than keeping it as a separate seasonal document.

    7. Plan for transport, utilities and critical supplies

    Practical adult social care winter planning addresses the energy supply, transport disruption and staff shortages that UKHSA identifies as business continuity risks. Map alternative travel routes, minimum critical stocks, priority premises checks and emergency contacts. For home care, consider how missed or delayed calls will be prioritised and communicated. For care homes, confirm heating maintenance and safe access arrangements.

    Do not rely on one supplier or one person holding essential contact details. Keep a controlled version that is available if normal systems or internet access are unavailable.

    8. Build one clear escalation route

    Adult social care winter planning needs defined triggers for internal escalation, commissioner notification and requests for mutual support. Examples include loss of heating, unsafe staffing, several missed calls, an outbreak or a sudden change in capacity. Each trigger should have an owner, contact route and recording requirement.

    Keep routine operational reporting separate from urgent safety escalation. Staff should be able to recognise the difference and know what to do when the usual manager is unavailable.

    9. Run a short test before September

    Testing adult social care winter planning through a thirty-minute desktop exercise can reveal more than another policy review. Use a plausible scenario, such as heavy snow combined with staff sickness and a heating fault. Ask who notices first, what is prioritised, how people are contacted, what evidence is recorded and when partners are told.

    Record actions with an owner and due date. Repeat the exercise after material changes. The aim is not a perfect script. It is evidence that the adult social care winter planning process works under pressure.

    A practical timetable from August to November

    WhenPriorityMinimum output
    By mid-AugustName the lead, confirm partners and update contacts.Owner and contact register.
    By the end of AugustShare capacity assumptions and complete the first scenario test.Capacity note and action log.
    During SeptemberClose actions, refresh staff briefings and check supplies.Completed evidence pack.
    During OctoberRecheck plans, alert distribution and individual risk controls.Signed review record.
    Before 1 NovemberDistribute the agreed cold-weather plan to managers and frontline staff.Version-controlled plan and briefing evidence.

    What good evidence looks like

    Good adult social care winter planning evidence is current, specific and usable. Keep the plan version, named owner, review date, contact list, capacity assumptions, scenario notes, action log and staff briefing record together. Where a contract or commissioner adds a local requirement, record the source and date rather than blending it into a generic policy.

    Care Sync Experts can help providers turn continuity, governance and winter-readiness expectations into practical systems through our compliance management service. If you want a focused review of your plan and evidence, book a Care Sync consultation.

    Frequently asked questions

    Do independent care providers have to meet the NHS 30 September 2026 assurance deadline?

    The NHS England letter assigns board assurance statements to integrated care boards and NHS providers. Independent care providers should not describe that as their direct deadline unless a commissioner, contract or other applicable instruction makes it relevant. Providers should still engage early because local draft plans are due by the end of August.

    When should an adult social care cold-weather plan be shared with staff?

    UKHSA says social care provider organisations should agree plans for managing cold-weather events and distribute them to managers and frontline staff before 1 November each year. Preparation should happen throughout the year.

    What should an adult social care winter plan cover?

    A practical plan should cover system contacts, capacity, discharge decisions, infection prevention, people at higher risk, staffing, transport, utilities, critical supplies, escalation and testing. The detail should reflect the service type and local arrangements.

    How should a home care provider prepare for severe cold weather?

    UKHSA recommends identifying people at higher risk, planning how to keep them warm, training staff to raise concerns, preparing for transport and staffing disruption, and arranging appropriate home checks during cold weather. The provider should define how delayed or missed calls will be prioritised and escalated.

    How often should a provider test its winter business continuity plan?

    Official guidance emphasises preparation and operational readiness but does not set one universal test frequency for every independent provider. Test before winter, after material changes and whenever an exercise or incident shows that arrangements may not work as intended.

    Evidence note: This guide was checked against current official NHS England and UKHSA sources on 9 August 2026. Guidance, local plans and contractual expectations can change, so check the latest guidance and your own commissioner instructions before acting.

  • Care Staff Supervision Records: What Registered Managers Should Document in 2026

    Care Staff Supervision Records: What Registered Managers Should Document in 2026

    Care staff supervision records should show what was discussed, what evidence was reviewed, what decisions were made, who owns each action and when progress will be checked. A signed form on its own is not enough. Registered managers need a reliable trail from the supervision conversation to safer practice, staff development and management follow-up.

    In England, CQC Regulation 18 guidance says staff must receive the support, training, professional development, supervision and appraisal necessary for their role. It also says staff should receive ongoing or periodic supervision so competence is maintained. The regulation does not set one universal timetable or one mandatory supervision form for every service.

    Why care staff supervision records matter

    Supervision is a management process, not a filing exercise. It gives the worker and supervisor protected time to review practice, workload, wellbeing, competence, learning and concerns. A good record helps the service demonstrate that it identified risks, agreed proportionate action and checked whether the action improved practice.

    The Skills for Care effective supervision guide describes supervision as a regular process for reviewing work. It says even informal supervision discussions should be recorded and added to existing notes. This matters because a quick conversation can contain an important decision, but memory alone is not a dependable governance control.

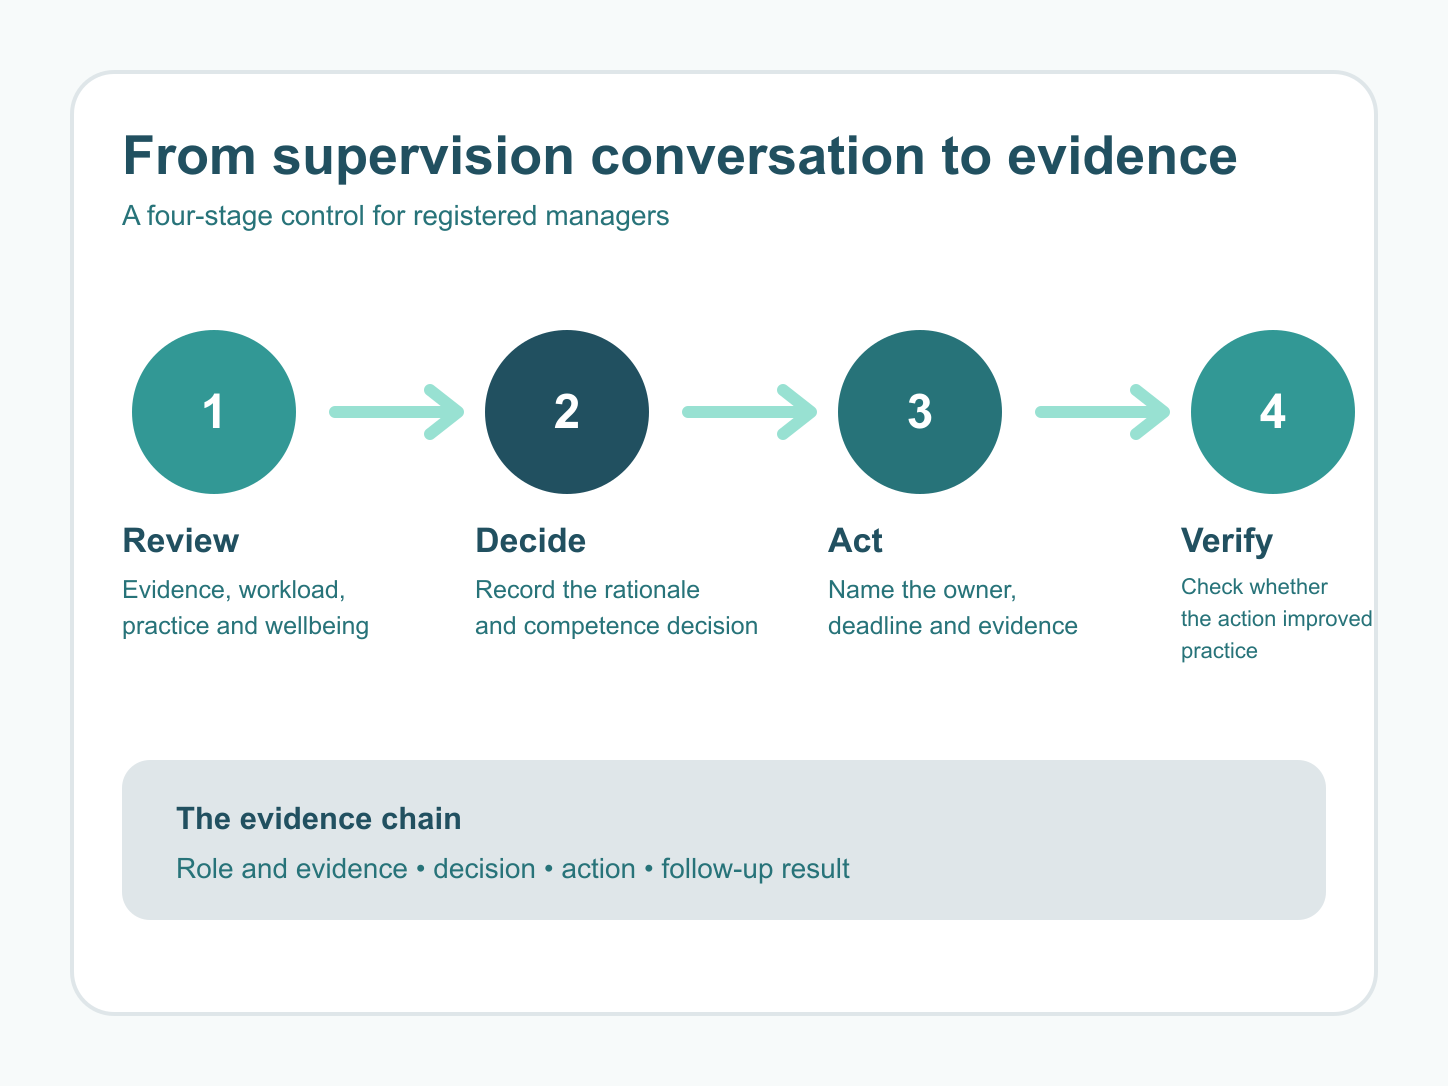
    Care staff supervision should therefore connect four things: the person’s role, the evidence reviewed, the decision reached and the follow-up. If any link is absent, the record may confirm that a meeting happened without showing what changed.

    Weak recordStronger recordWhy it matters
    Discussed trainingReviewed moving and handling observation dated 28 July; refresher booked for 14 AugustConnects the discussion to evidence and action
    No concernsWorker raised no new concerns; safeguarding and whistleblowing routes were checkedShows what was tested rather than relying on a vague conclusion
    Improve documentationThree daily notes sampled; manager identified missing outcome detail and set a coached-recording reviewDefines the practice gap and how improvement will be checked

    Nine essential care staff supervision records for 2026

    1. Session identity and purpose

    Record the worker, supervisor, date, time, format and purpose of the session. Note whether it is planned, return-to-work, probationary, capability-focused or an additional risk-led meeting. Keep the title neutral and accurate.

    2. Agenda and preparation evidence

    List the agenda and the records considered before or during the session. These may include observations, spot checks, complaints, compliments, training records, care documentation audits and previous actions. Only include records that were genuinely reviewed.

    3. The worker’s account

    Capture the worker’s explanation, reflections and questions fairly. Separate what the worker reported from what the supervisor observed or concluded. If accounts differ, record both and identify what further evidence or process is needed.

    Care staff supervision records workspace with an anonymised form, action tracker and competence checklist

    4. Practice and outcomes reviewed

    Record the practice evidence sampled and what it showed. Use specific, proportionate examples without copying unnecessary information about people receiving care into an employment record. Where concerns relate to care delivery, follow the correct safeguarding, incident or quality process as well.

    5. Competence decision

    State the task or responsibility assessed, the evidence used and the decision. Training attendance is not the same as observed competence. If direct observation is required, record who will carry it out, the standard to be used and what happens until competence is demonstrated.

    6. Learning and development plan

    Link identified needs to role-specific learning, coaching, shadowing or assessment. Give each activity an owner and target date. Care Sync’s comprehensive training support for care providers can help organisations connect training plans with practical development needs.

    7. Wellbeing, workload and support

    Give the worker space to discuss workload, support needs and factors affecting their role. Record only what is necessary and relevant. Where health information is involved, use the organisation’s data protection, occupational health and HR processes. The ICO employment information guidance explains that worker records are subject to UK GDPR and the Data Protection Act 2018.

    8. Actions, owners and deadlines

    Write each action so another authorised manager can understand it. State what will be done, who owns it, the target date and the evidence needed to close it. Avoid vague actions such as monitor, improve or keep under review without a defined test.

    9. Agreement, amendments and next review

    Record whether the worker received the notes, whether they requested corrections and how any disagreement was preserved. Include the next planned review or an earlier follow-up date where risk or development actions require it. A signature confirms receipt or participation only if your policy says so; it should not be presented as automatic agreement with every conclusion.

    How often should care staff supervision take place?

    There is no single CQC interval that fits every worker and service. Your policy should set a defensible baseline and allow additional supervision when the person’s experience, time in role, complexity of work, support needs or current risks require it. Skills for Care identifies these as relevant factors when deciding frequency and length.

    A new starter, a worker learning a delegated task or someone returning after a long absence may need closer supervision. An experienced worker may still need an earlier session after a complaint, incident, practice concern, role change or significant learning need. The reason for changing the frequency should be recorded.

    TriggerManagement responseRecord to retain
    New role or probationSet closer review points and observation opportunitiesRole expectations, evidence reviewed and next checkpoint
    New or delegated taskSupervise until acceptable competence is demonstratedAssessment standard, observation outcome and delegation decision
    Complaint or incident learningUse the correct formal process and bring relevant learning into supervisionProportionate cross-reference, action and follow-up evidence
    Stable performanceMaintain the policy baseline and periodic competence checksBalanced review of strengths, learning and objectives

    Turning supervision notes into evidence of improvement

    The most useful care staff supervision record is not the longest. It is the one that helps the manager answer three questions quickly: What did we learn? What did we decide? Did the action work?

    Four-stage care staff supervision evidence chain from review and decision to action and follow-up
    1. Open the previous actions. Mark each as complete, carried forward or overdue, with evidence.
    2. Review a balanced evidence set. Include strengths and positive feedback as well as gaps.
    3. Write decisions, not transcripts. Retain the material facts, the worker’s account and the management rationale.
    4. Route formal matters correctly. Supervision notes should not replace safeguarding, grievance, disciplinary or incident procedures.
    5. Close the loop. Sample the agreed practice or record after the action date and record the result.

    This evidence chain also supports role clarity. Our Care Workforce Pathway Part 3 guide explains how supervision and practice leadership connect to competence and development. The registered manager and nominated individual guide separates daily operational control from provider-level oversight.

    Keep supervision separate from appraisal and formal processes

    Supervision, appraisal, disciplinary action, grievance handling and safeguarding each serve different purposes. A service may refer to the same underlying event in more than one process, but the record should make clear which process is being used and why. A routine supervision note should not become an informal substitute for a fair disciplinary investigation or a safeguarding referral.

    Appraisal normally takes a wider and longer-term view of performance, objectives and development. Supervision is usually more frequent and focuses on current practice, support and immediate actions. Keeping the two distinct helps managers avoid postponing urgent matters until an annual review and prevents an appraisal record from becoming overloaded with operational detail.

    If a concern emerges during care staff supervision, record the concern in neutral terms, note any immediate safety action and identify the formal route used next. Do not record a final finding before the relevant process has been completed. Where the worker disagrees, preserve their account and avoid language that treats an allegation as an established fact.

    Issue raised in supervisionImmediate recordNext route
    Possible safeguarding concernMaterial facts, immediate protection and escalation timeSafeguarding procedure and external notification where required
    Possible misconductNeutral summary and any proportionate interim controlHR and disciplinary procedure
    Worker grievanceThe worker’s concern and how it was acknowledgedGrievance procedure
    Learning or confidence gapTask, evidence, support need and agreed actionDevelopment plan, coaching and competence review

    Record defensible competence decisions

    A competence decision should identify the task, the evidence and the decision maker. Course attendance can support the decision, but it does not by itself show that a worker can perform safely in practice. Depending on the task, evidence may include direct observation, a discussion of scenarios, a documentation sample, feedback or a supervised demonstration.

    Write the decision precisely. State whether the worker is competent to practise independently, requires further supervised practice or must not perform the task until a defined assessment is completed. Name any temporary control, such as shadowing or second checking, and set the review date. This makes the care staff supervision record useful to authorised managers who need to allocate work safely.

    Weak actionStronger actionClosure evidence
    Improve medicines knowledgeComplete medicines refresher by 18 August, then undertake a directly observed round with the deputy managerTraining record, observation checklist and recorded competence decision
    Monitor record keepingSupervisor will sample five daily notes on 20 August against the service recording standardAudit result, feedback provided and any follow-up action
    More support neededArrange two shadow shifts with the named senior, followed by a review on 25 AugustShadowing feedback and review outcome

    Protect confidentiality and control access

    Care staff supervision records are employment records. They may also contain health information, allegations or information about people receiving care. Record only what is necessary for the management purpose, avoid copying whole incident or care records, and use a proportionate cross-reference where the detailed evidence is held in the correct system.

    Access should be limited to authorised people with a genuine need to know. The service should define where records are stored, who can view or amend them, how amendments are tracked and how long records are retained. These controls should align with the organisation’s current privacy information, retention schedule and employment-record procedures.

    Before sharing a record, check whether the recipient needs the full note or only a specific action. Sensitive information should not be copied into general rotas, handover notes or open action trackers. If a supervision action affects safe deployment, managers still need a reliable way to communicate the operational restriction without disclosing unnecessary personal detail.

    A practical first 30 days for registered managers

    Days 1 to 7: test the current system

    Compare the supervision schedule with completed records for a small, representative sample. Include new starters, experienced workers, night staff, agency-facing roles and anyone with an open development action. Record gaps without assuming their cause. Check whether postponed sessions have an authorised reason and a new date.

    Days 8 to 14: strengthen the template

    Review whether the template prompts supervisors to cite evidence, record the worker’s account, make a competence decision and assign actions. Remove prompts that encourage unnecessary personal detail. Keep enough flexibility for role-specific discussion rather than forcing every session into identical wording.

    Days 15 to 21: calibrate supervisors

    Use anonymised examples to agree what strong evidence and clear actions look like. Check that supervisors understand the boundaries between routine supervision and formal procedures. Give them an escalation route for uncertainty, especially where safeguarding, health information or possible misconduct is involved.

    Days 22 to 30: close actions and report themes

    Review overdue actions, sample closure evidence and identify themes across teams. Separate individual matters from service-wide learning. Report material gaps through the provider’s governance route and set the next audit date. The aim is a repeatable control, not a one-off document tidy-up.

    At the end of the first month, keep a short improvement log. Record the original gap, the change made, the evidence sampled and the result. This gives the registered manager a clear basis for deciding whether the new control is working. If the sample still shows missed sessions, vague decisions or overdue actions, adjust supervisor support and repeat the test. Do not mark the work complete merely because a revised template has been issued.

    A monthly supervision record audit for registered managers

    Seven-point monthly care staff supervision record audit for registered managers
    • Compare the supervision schedule with completed records and approved postponements.
    • Sample whether previous actions were reviewed before new actions were added.
    • Check that competence decisions identify the task, evidence and decision maker.
    • Confirm safeguarding, disciplinary and grievance issues were routed through the proper process.
    • Check access controls for employment records, particularly health or other sensitive information.
    • Test whether overdue actions are visible to the responsible manager.
    • Record themes that require service-wide learning, training or quality action.

    Use trends carefully. A missed meeting may be an isolated scheduling problem or part of a wider control weakness. Record what the audit shows, investigate the cause and avoid turning an unexplained gap into a conclusion about an individual.

    How Care Sync Experts can help

    Care Sync Experts can help providers strengthen supervisor capability, training plans and the link between learning and practice. We can review whether your supervision process produces clear actions, proportionate evidence and useful management oversight.

    If you want practical support to improve your supervision framework or develop managers, book a consultation with Care Sync Experts.

    Frequently asked questions

    What should a care staff supervision record include?

    Include the session details, agenda, evidence reviewed, the worker’s account, practice and competence decisions, development needs, support offered, agreed actions, owners, deadlines and follow-up date. Keep the record accurate, proportionate and linked to evidence.

    How often should care staff supervision take place?

    Set a policy baseline, then adjust it according to experience, time in role, work complexity, support needs and risk. CQC requires necessary ongoing or periodic supervision, but does not prescribe one universal interval for every care worker.

    Can informal catch ups count as supervision?

    Informal discussions can support day-to-day management, but they should not automatically replace the structured supervision required by your policy. Skills for Care recommends recording informal supervision discussions and adding them to existing notes.

    Should supervision notes include health information?

    Only record information that is necessary for the employment and support purpose. Health information needs particular care, lawful handling and appropriate security. Follow current ICO guidance and your organisation’s HR, privacy and occupational health procedures.

    Who is accountable when supervision is delegated?

    A trained and competent supervisor may carry out sessions, but the registered manager remains responsible for ensuring that an effective supervision system operates in the regulated service. Delegation should include clear authority, escalation routes and quality checks.

    How can registered managers audit supervision records?

    Compare the schedule with completed sessions, sample whether evidence supports decisions, check action closure, test confidentiality and review themes across the service. Record the audit date, sample, findings, actions and named owner.

    Official source check completed 4 August 2026. Check the latest CQC Regulation 18 guidance, Skills for Care supervision guidance and ICO employment information guidance before changing policy or record-retention controls.

  • Dementia Support Service Tender 2026: Birmingham and Solihull Bid Guide

    Dementia Support Service Tender 2026: Birmingham and Solihull Bid Guide

    The Dementia Support Service tender seeks one provider to deliver a coordinated service across Birmingham and Solihull. NHS Birmingham and Solihull Integrated Care Board has stated an estimated value of £3,336,000 excluding VAT, with submissions due by 5pm on 29 July 2026.

    This is a specialist community health service, not a routine domiciliary care contract. The successful provider will need to show how people living with dementia, their carers and families will receive timely information, practical support, effective navigation and joined-up referral pathways.

    The official Dementia Support Service tender notice on Find a Tender confirms a single lot for Birmingham, an open procedure and a quality weighting of 90 per cent. The detailed conditions of participation and service requirements remain in the Atamis procurement documents, so bidders should search for project reference C387762 before making a final bid decision.

    In this guide: we explain the service scope, contract structure, bidder fit, evidence priorities and practical steps required to prepare a credible response to the Dementia Support Service tender.

    Key Takeaways

    • The opportunity is a single-lot community health procurement covering Birmingham and Solihull.
    • Technical quality carries 90 per cent of the published weighting, so pathway design and verified evidence are central to the response.
    • The Dementia Support Service tender does not publicly state that CQC registration is mandatory. Bidders must confirm all conditions in Atamis.
    • A credible bid needs specialist dementia capability, equitable access, local partnerships, carer support, lived experience and measurable outcomes.

    Dementia Support Service Tender at a Glance

    • Buyer: NHS Birmingham and Solihull Integrated Care Board
    • Procurement support: NHS Arden and Greater East Midlands Commissioning Support Unit
    • Project reference: C387762
    • Procurement ID: ocds-h6vhtk-060f00
    • Procedure: open procedure
    • Regime: Procurement Act 2023, light touch contract
    • Lots: one
    • Delivery area: Birmingham, with the service covering Birmingham and Solihull
    • Estimated value: £3,336,000 excluding VAT
    • Stated annual value: £834,000
    • Initial term: 1 January 2027 to 31 December 2028
    • Extension: up to two further years, to 31 December 2030
    • Quality weighting: 90 per cent
    • Price weighting: 10 per cent
    • Submission deadline: 5pm on 29 July 2026
    • Submission portal: Atamis

    The public enquiry deadline was 5pm on 17 July 2026, which has passed. Bidders should still review every published clarification and document version in Atamis before submission. Review the Dementia Support Service tender record on Care Sync Experts for a convenient summary, then use the buyer’s portal as the final authority. You can also browse our wider feed of healthcare tender opportunities.

    What Service Is the Buyer Commissioning?

    The buyer wants a single point of access for information and advice about dementia, including support available before and after diagnosis and clear guidance on how people can access it.

    The public notice describes a service that should provide or facilitate:

    • signposting to relevant support services and community groups;
    • practical emotional support that helps people feel safer and more resilient;
    • coaching for people living with dementia and their carers, tailored to their circumstances;
    • access to peer-led group support;
    • person-centred support that promotes independence and wellbeing;
    • better coordination across health, social care and voluntary sector partners;
    • proactive intervention intended to reduce avoidable crises, hospital admissions and delayed discharges;
    • meaningful involvement of lived experience in service design, delivery and evaluation;
    • clear referral pathways into, through and out of the service;
    • equitable access across different communities and areas of Birmingham and Solihull.

    This scope aligns with the local Birmingham and Solihull Dementia Strategy 2023 to 2028, which prioritises information, timely diagnosis with support, crisis prevention and personalised care planning. A strong tender response should connect its delivery model to these local priorities without simply repeating strategy language.

    Dementia Support Service tender discussion with an older woman, family member and community service navigator
    The proposed service must make information, navigation and practical support easier to access for people living with dementia and those who support them.

    Who Is This Tender Likely to Suit?

    The opportunity is likely to suit established dementia charities, voluntary and community organisations, community health providers, social care organisations and partnerships that can demonstrate relevant specialist experience at scale.

    The notice identifies the opportunity as particularly suitable for small and medium-sized enterprises and voluntary, community and social enterprises. That does not remove the need to prove capacity, governance, financial resilience and safe mobilisation for a contract of this size.

    A domiciliary care or supported living provider may have relevant experience, but it should not assume that care delivery or CQC registration alone proves suitability. The public notice does not state that CQC registration is a condition of participation. The detailed procurement documents must be checked before making any claim about mandatory registration, accreditations, turnover thresholds or insurance levels.

    Before bidding, leadership should be able to evidence:

    • specialist knowledge of dementia and its impact on people, carers, families and communities;
    • a credible single point of access and navigation model;
    • strong local partnerships and referral arrangements across Birmingham and Solihull;
    • accessible delivery for diverse communities and people affected by health inequalities;
    • a competent, supervised and resilient workforce;
    • safe information sharing, safeguarding and risk management;
    • measurable outcomes and reliable performance reporting;
    • mobilisation capacity for a 1 January 2027 start;
    • financial sustainability at the proposed price.

    If your team is new to public procurement, read our guide to tenders in health and social care before building the compliance matrix.

    Why the 90 Per Cent Quality Weighting Matters

    The published award criteria allocate 90 per cent to technical quality and 10 per cent to commercial cost. This makes the evidence, clarity and credibility of the delivery solution central to the competition.

    It does not mean price can be ignored. A low quality response will struggle, but an unsustainable or poorly evidenced cost model can still damage the submission. Bid teams should align the service model, staffing assumptions, activity volumes, partnership commitments and price before final drafting.

    The notice directs suppliers to the procurement documents for the detailed quality criteria. Do not invent sub-weightings or assume the final questions. Build the response plan from the latest Atamis pack, including every schedule, declaration, word limit and clarification.

    Watch: Three Hidden Healthcare Tender Eligibility Checks

    Our Care Sync Experts video explains three checks that can stop a healthcare bid before evaluators reach the method statements. Use it as a decision prompt for the Dementia Support Service tender, then verify every requirement against the current Atamis pack.

    Watch the healthcare tender eligibility video on YouTube

    Eight Evidence Areas to Prepare

    1. A clear person-centred pathway

    Map the journey from first contact to triage, information, support planning, intervention, onward referral and exit. Explain choice, consent, accessibility, handovers and what happens when a person’s needs change.

    The NICE dementia guideline places the person’s individuality, perspective, relationships and wellbeing at the centre of good practice. Use this as a clinical and practice reference, then show exactly how your operating model will deliver it.

    2. Local access and health inequalities

    The notice expects the service to consider geographical demand, population differences and dementia prevalence across Birmingham and Solihull. A generic city-wide claim is not enough. Show where and how people will access the service, including communities that may experience language, cultural, digital, transport or trust barriers.

    3. Referral pathways and partnership governance

    Identify likely referral partners, their roles, handover standards and escalation routes. Distinguish a supportive relationship from a formal commitment. Any letters of support should be current, specific and consistent with the proposed delivery model.

    4. Support for carers and families

    Explain how carers will receive information, practical coaching, emotional support and appropriate onward referral whilst protecting the rights and wishes of the person living with dementia. Show how the service will recognise carer strain and respond proportionately.

    5. Lived experience and co-production

    The notice calls for lived experience to be embedded in design, delivery and evaluation. Define who will participate, how their contribution will be supported, how feedback will influence decisions and how you will report the changes made.

    6. Workforce competence and supervision

    Set out roles, caseload assumptions, specialist competencies, induction, ongoing learning, supervision and cover arrangements. The workforce plan should connect directly to activity, geography, opening hours and the needs of diverse communities.

    7. Outcomes, data and learning

    Separate service activity from meaningful outcomes. Contact volumes and referrals are useful measures, but the buyer will also need confidence that the service improves access, wellbeing, independence, coordination and crisis prevention. Define data quality controls and how learning will change practice.

    8. Mobilisation and continuity

    Work backwards from 1 January 2027. Cover governance, recruitment, technology, information governance, referral testing, partner onboarding, communications, training, readiness reviews and business continuity. Give each dependency an owner and decision date.

    Care Sync Experts can help turn the procurement pack into a traceable response plan through our healthcare tender writing service.

    How to Turn the Dementia Support Service Tender Quality Weighting Into Scorable Evidence

    The 90 per cent technical weighting makes the quality narrative central, but evaluators can only score what the response demonstrates. A strong bid should create a traceable line from each requirement to the delivery method, accountable role, evidence source and measurable outcome. The controls below help prevent specialist knowledge from becoming a set of unscored general statements.

    Show the pathway, not only the service values

    Values such as compassion, choice and person-centred support matter, but they need an operating method. Explain how a person or carer enters the service, receives accessible information, is triaged, agrees priorities, accesses support and moves between services. Include decision points, handovers, consent, safeguarding and exit planning. This gives evaluators a usable picture of the experience rather than asking them to infer it.

    Use evidence that matches the commitment

    For each important promise, identify evidence of relevant delivery. A case example may demonstrate practice, performance data may demonstrate consistency and a policy may demonstrate organisational control. None of these sources should be stretched beyond what it proves. Where direct evidence is limited, explain the gap, the transferable element and the mobilisation control. Do not present an unrelated care contract as proof of specialist dementia navigation.

    Define local partnership accountability

    A partnership list is not a pathway. Name the likely role of each partner, referral direction, information exchange, governance route and escalation point. Separate confirmed commitments from relationships that still need to be established. The mobilisation plan should show when agreements will be completed, how the pathway will be tested and what happens if a dependency is delayed.

    Connect outcomes to service activity

    Explain how contacts, referrals and group attendance contribute to outcomes that matter to people living with dementia and carers. Define the measure, data source, review frequency and person responsible for quality assurance. Include how feedback and lived experience will change the service, not simply how they will be collected. This helps demonstrate that performance management will support learning rather than becoming a reporting exercise.

    Complete an independent evaluator review

    A reviewer who did not draft the response should check whether every question has been answered, every claim can be verified and every commitment is reflected in staffing and price. Flag vague phrases such as seamless support or strong partnerships unless the method immediately follows. A separate compliance review should confirm declarations, attachments, word limits, filenames and the latest Atamis document versions before upload.

    What the Light Touch Open Procedure Means

    The notice classifies the procurement as a light touch contract under the Procurement Act 2023 and uses an open procedure. Government light touch contract guidance explains that these services are subject to a more flexible regime, whilst open procedure guidance describes a single-stage competition in which any supplier may submit a tender.

    For a bidder, the practical point is simple: do not mistake procedural flexibility for relaxed evidence requirements. The buyer has published a competitive opportunity, and the response must meet the conditions, instructions and evaluation criteria in the procurement pack.

    A Practical Bid Preparation Plan

    1. Confirm the live pack: access Atamis, search C387762 and record every document version and clarification.
    2. Run the bid decision: test specialist fit, local delivery capacity, partnerships, evidence, price and mobilisation risk.
    3. Build a compliance matrix: map every question, attachment, declaration, limit, criterion and owner.
    4. Lock the service model: agree the pathway, access routes, workforce, governance, partnerships, outcomes and information flows.
    5. Validate evidence: use current examples, data and documents that directly support each claim.
    6. Reconcile solution and price: check that staffing, volumes, overheads, partnership costs and performance commitments are financially consistent.
    7. Review independently: complete factual, compliance, evaluator, financial and presentation reviews.
    8. Submit early: verify every upload and retain the portal receipt before 5pm on 29 July 2026.

    Common Reasons a Dementia Support Service Bid Could Lose Marks

    • describing generic dementia awareness rather than a working service pathway;
    • claiming partnerships without named roles, referral processes or accountability;
    • treating lived experience as a consultation exercise with no influence on delivery;
    • failing to explain equitable access across Birmingham and Solihull;
    • using activity counts as substitutes for outcomes;
    • presenting workforce numbers that do not match geography, demand or opening hours;
    • ignoring carers, crisis prevention or coordination with other services;
    • guessing requirements that are only available in the Atamis documents;
    • allowing the cost model and delivery narrative to contradict each other;
    • submitting against an old document version or missing a mandatory attachment.

    A disciplined response makes each requirement easy to find and each material claim easy to verify. Our article on public contract readiness for smaller providers provides further context for building a stronger evidence base.

    Should Your Organisation Bid?

    Bid for the Dementia Support Service tender if you can demonstrate specialist dementia support capability, a realistic local delivery model, credible partnerships, a robust workforce, measurable outcomes and sustainable pricing.

    Consider a no-bid decision if the organisation would need to invent local capacity, rely on unconfirmed partners, stretch unrelated care experience to fit the requirement or mobilise a service model it has not costed properly.

    Before approving the bid, leadership should be able to answer:

    1. Why are we a strong fit for this exact service?
    2. What evidence proves our pathway will work across Birmingham and Solihull?
    3. Which gaps remain, and can they be closed before submission and mobilisation?
    4. Can we deliver every commitment safely and sustainably at our proposed price?

    Need Support With the Dementia Support Service Tender?

    Care Sync Experts can help you review the Dementia Support Service tender, build the compliance matrix, strengthen evidence and prepare a clear, evaluator-friendly tender response. We will also tell you when the available evidence supports a no-bid decision.

    Book a tender consultation to discuss your current evidence and submission timetable.

    This article is an independent summary based on the public notice and official guidance available on 19 July 2026. It is not the procurement pack and does not replace Atamis documents, buyer clarifications or professional legal advice.

    Frequently Asked Questions

    What is the deadline for the Dementia Support Service tender?

    The official Dementia Support Service tender notice states that tenders must be submitted by 5pm on 29 July 2026. Bidders should confirm the live deadline and any formal amendment in Atamis.

    How much is the contract worth?

    The estimated value is £3,336,000 excluding VAT. The notice also states an annual value of £834,000 and provides an initial two-year term with an option to extend for up to two further years.

    Is CQC registration required?

    The public notice does not state that CQC registration is a condition of participation. Bidders must check the full procurement documents before deciding which registrations, accreditations and evidence are mandatory.

    Can an SME or voluntary organisation bid?

    Yes. The notice identifies the opportunity as particularly suitable for SMEs and voluntary, community and social enterprises. Every bidder must still meet the published conditions and demonstrate capacity to deliver the full contract.

    How will the tender be evaluated?

    The published criteria allocate 90 per cent to technical quality and 10 per cent to cost. The detailed questions, scoring method and sub-criteria must be taken from the current Atamis documents.

  • Adult Social Care Fair Pay Agreement: What Care Providers Should Prepare for Before 2028

    Adult Social Care Fair Pay Agreement: What Care Providers Should Prepare for Before 2028

    The adult social care Fair Pay Agreement is intended to set negotiated minimum pay and employment terms for much of England’s paid adult social care workforce from April 2028. The rate has not been decided. Providers should prepare evidence, systems and cost scenarios now, without changing pay on the basis of an unknown future figure.

    The most useful preparation is operational: identify which roles may be in scope, clean payroll and workforce data, test cost assumptions, review contracts, prepare commissioner evidence and give the board a controlled readiness plan. This guide turns the confirmed policy timetable into seven practical provider actions.

    Social Care Fair Pay Agreement: Confirmed Facts and Open Questions

    The government published its response to the adult social care Fair Pay Agreement consultation on 16 July 2026. The policy applies to England. It is a future negotiating system created under the Employment Rights Act 2025, not a new pay rate that providers must apply today.

    Confirmed positionWhat is not yet decidedProvider implication
    An Adult Social Care Negotiating Body will bring together equal worker and employer representation.The first negotiated pay level and detailed employment terms.Prepare accurate workforce and cost evidence, but do not budget against a guessed rate.
    The Trades Union Congress will coordinate worker representation and the Care Provider Alliance will coordinate employer representation.The detailed composition, appointment process and operating procedures of the body.Follow updates from the recognised representative bodies and official government channels.
    Local government will have a formal advisory and evidence role, without a vote on final agreements.How individual commissioning authorities will translate national funding and terms into local fees and contracts.Build a commissioner-ready evidence pack before fee discussions begin.
    The government has identified a £500 million funding envelope for the first year.How that funding will flow through local government, contracts and provider fees in each area.Do not treat the national envelope as a guaranteed organisation-level allocation.
    Regulations are expected in 2026, appointments during 2026 to 2027, negotiations around April 2027 and the first agreement from April 2028.The final agreement’s exact scope, implementation guidance and enforcement detail.Use staged readiness gates and refresh assumptions when regulations and guidance are published.

    The government response on the Fair Pay Agreement process is the controlling current source for the design and timetable. The related Department of Health and Social Care announcement summarises the intended worker voice and first-year funding commitment.

    The government says the future agreement can cover pay and terms and conditions. Negotiators may also consider training, career progression, people and culture, and additional benefits. Those areas are possible parts of the remit, not settled terms. Providers should record them as issues to monitor rather than commitments already made.

    Who is expected to be in scope?

    The current policy covers the paid adult social care workforce within the statutory scope in England. The government’s response says workers already covered by Agenda for Change, the NHS Pay Review Body or National Joint Council arrangements are excluded. Unpaid carers, self-employed workers and informal care arrangements are outside the current coverage.

    Mixed roles need care. A worker may split time between regulated care, administration, domestic work or another service. The correct approach is to record actual duties, contractual arrangements, hours and pay components, then test the position against the final regulations and guidance. A job title alone is not reliable evidence.

    The 2026 to 2028 Fair Pay Agreement Timeline

    The timetable gives providers a planning window, but it should be treated as a sequence of evidence gates. Each official milestone may refine earlier assumptions.

    PeriodExpected policy milestoneProvider readiness gate
    2026Secondary regulations are expected to be laid.Confirm the legal scope, definitions, governance and any evidence requirements. Update the provider risk register.
    2026 to 2027The Negotiating Body is established and representatives are appointed.Nominate internal owners, engage through recognised sector bodies and document workforce priorities.
    Around April 2027The first negotiation period is expected to begin.Refresh cost scenarios, workforce data and commissioner evidence using the published remit.
    Six-month negotiation periodWorker and employer representatives negotiate the first agreement.Track confirmed developments, separate official information from commentary and log decision impacts.
    Six-month implementation periodProviders and commissioners prepare to implement a ratified agreement.Complete payroll, contract, communication and assurance changes only against the final ratified terms.
    April 2028The government intends the first agreement to take effect.Verify implementation, worker communications, contractual incorporation, funding assumptions and ongoing compliance evidence.

    The dates are the government’s intended sequence at the time of checking, not a promise that every operational detail will arrive on a fixed day. Add a policy watch to the board calendar and assign one owner to verify changes against the official response, regulations and subsequent Department of Health and Social Care guidance.

    7 Practical Steps for Social Care Fair Pay Agreement Readiness

    1. Establish a controlled workforce scope register

    Start with every paid role that contributes to adult social care delivery. Record the legal employer, service, location, contract type, employment status, main duties, secondary duties, hours pattern, commissioning route and current pay components. Flag workers whose duties cross more than one service or occupational group.

    Do not decide final coverage yourself before regulations are available. Use statuses such as likely in scope, likely excluded and requires clarification. Record the evidence and the source date behind each classification. That creates an auditable decision trail and makes later corrections manageable.

    2. Reconcile payroll, rota and HR data

    A future agreement may affect more than a headline hourly rate. Providers need a reliable view of basic pay, enhancements, sleep-in arrangements, overtime, travel time, training time, contracted hours, variable hours, allowances and benefits. Reconcile these fields across payroll, contracts, rotas and HR records.

    Keep present legal compliance separate from future policy preparation. The current statutory pay floor remains governed by minimum wage law. Care Sync’s National Minimum Wage 2026 guide for care providers explains the current control questions around working time and records.

    Adult social care fair pay agreement readiness workspace with role, payroll and evidence cards
    Bring role, payroll, rota and contract evidence into one controlled readiness record.

    3. Model scenarios without inventing the future rate

    Use a variable, not a prediction. Build scenarios that show how different changes to basic pay, differentials, employer on-costs and paid working time would affect the organisation. Show assumptions separately and include sensitivity ranges. Never present a scenario as the government’s proposed rate.

    Include employer National Insurance, pension contributions, holiday pay, overtime interactions, agency exposure, supervision capacity and any effect on pay differentials. A rise at the lowest point of a pay structure may create compression between care workers, senior carers, supervisors and managers. That is a workforce design issue as well as a payroll cost.

    4. Map contracts and commissioning exposure

    List each material income stream and contract. Record the commissioner, payment mechanism, annual review clause, change-control route, indexation method, notice requirements, open-book provisions, service volumes and current expiry date. Identify contracts that may not automatically recognise new workforce costs.

    The government’s £500 million first-year envelope is not ringfenced as a direct payment to each provider. Local fee mechanisms and contract changes still matter. Providers should avoid assuming that a national funding announcement will automatically cover every additional cost in full.

    5. Prepare commissioner-ready evidence

    Commissioners need evidence they can understand and test. A useful pack contains a workforce baseline, pay structure, affected hours, on-cost assumptions, contract references, service-level impact and a clear reconciliation between payroll data and the funding request. Show the effect by contract or service where possible.

    The Local Government Association’s Fair Pay Agreement information confirms local government’s advisory and evidence role. That makes clear, consistent provider information valuable, even though councils will not vote on the final national agreement.

    Adult social care leaders reviewing fair pay agreement workforce and cost scenarios
    Use transparent assumptions so commissioners and leaders can trace every cost scenario back to workforce evidence.

    6. Put governance and communications in place

    Assign executive or provider-level accountability, an operational lead, a finance lead and an HR or employment-law lead. Define what each person can decide and which changes require board or owner approval. Keep a dated source register so policy commentary does not become an undocumented instruction.

    Tell staff what is known, what remains undecided and when the next update is due. Avoid implying that a specific increase has been agreed. Once an agreement is ratified, government guidance indicates that it will become part of covered workers’ contracts. Contractual implementation should therefore follow the final terms and proper employment advice.

    7. Build an implementation rehearsal

    Before the final agreement arrives, rehearse the process using sample rate variables rather than invented figures. Test whether payroll fields can be changed accurately, whether contract clauses can be identified, whether worker groups can be segmented and whether the organisation can produce a commissioner evidence pack quickly.

    The rehearsal should produce exceptions, owners and completion dates. It should not change live pay or employee contracts. Use the result to strengthen compliance management controls, data quality and decision evidence before the statutory implementation window.

    Fair Pay Agreement Workforce and Payroll Evidence Matrix

    This matrix helps providers connect each readiness decision to evidence. It is a Care Sync operational model, not a prescribed government template.

    Readiness questionEvidence to retainOwnerControl test
    Which workers may be covered?Employment contract, role profile, actual duties, service assignment and employment statusHR and operationsCan every classification be traced to dated evidence?
    What hours and pay elements apply?Payroll extract, rota, timesheets, travel records, training records, sleep-in and overtime dataPayroll and financeDo payroll totals reconcile to worked and paid time?
    What would a change cost?Scenario model, assumptions, employer on-costs, pay differentials and service volumesFinanceCan another reviewer reproduce the calculation?
    Which contracts may need action?Commissioning contract, fee schedule, review clause, change-control process and expiry dateCommercial or provider leadIs the route for requesting a fee or contract change documented?
    How will workers be informed?Communication plan, approved messages, consultation records and question logHR and leadershipDoes every message distinguish confirmed facts from unresolved terms?
    How will implementation be assured?Change plan, payroll checks, contract updates, exception log and board sign-offNamed accountable leadHas a second person checked affected workers and calculated values?

    Data protection still applies. Limit access to identifiable employee data, use role-based permissions and share aggregated information where individual records are not required. A readiness project is not a reason to duplicate sensitive workforce files across uncontrolled spreadsheets.

    Commissioner Conversation Checklist

    Providers do not need to wait until 2028 to improve the quality of commissioning conversations. The aim now is to understand the evidence route and reduce surprises, not to negotiate against an unconfirmed rate.

    • Confirm the local contact. Identify who owns adult social care workforce funding, contract change and fee-review discussions.
    • Ask about the evidence format. Clarify whether the authority expects contract-level, service-level or organisation-level information.
    • Record the contractual route. Note notice periods, review dates and the change-control mechanism for every major contract.
    • Agree baseline definitions. Make sure hours, full-time equivalents, pay components and on-costs are interpreted consistently.
    • Separate fact from scenario. Label all modelled figures and state that the first negotiated rate is not yet known.
    • Track unresolved funding questions. Record what is awaiting national guidance, what requires local clarification and who will follow up.
    • Preserve an audit trail. Keep dated notes, source documents, submitted evidence and commissioner responses.

    The Care England Fair Pay Agreement hub is a useful provider-sector monitoring route. It does not replace regulations or government guidance, but it can help leaders follow employer representation and sector engagement.

    A Board Dashboard for Fair Pay Agreement Readiness

    Senior oversight should be short, factual and decision-focused. A monthly or quarterly dashboard can use the following six controls.

    ControlGreen evidenceEscalation trigger
    Policy watchOfficial sources checked on schedule with changes loggedNew regulation or guidance has not been assessed
    Workforce scopeRoles classified with evidence and exceptions recordedMaterial worker groups have incomplete or conflicting records
    Payroll integrityPay elements and hours reconcile across systemsUnexplained differences affect cost modelling
    Financial scenariosAssumptions are version-controlled and independently checkedA scenario is being treated as an agreed future rate
    Contract exposureReview and change routes are known for material contractsA high-value contract has no viable cost-recovery route
    CommunicationsStaff messages state confirmed facts and open questionsManagers are making inconsistent pay commitments

    Governance should focus on readiness quality, not activity volume. The number of meetings held is less useful than whether the workforce register is complete, payroll data reconciles, assumptions are controlled and contract routes are understood.

    How Care Sync Experts Can Help

    Care Sync Experts can help providers turn the emerging Fair Pay Agreement into a controlled readiness programme. Support can include workforce and evidence mapping, compliance governance, action tracking, document alignment, commissioner evidence preparation and independent review of the implementation plan.

    If you want an evidence-led review of your workforce scope, payroll controls, contract exposure or governance plan, book a consultation with Care Sync Experts. Where contractual, tax or employment-law decisions are required, use appropriately qualified legal or accountancy advice alongside operational support.

    Evidence note: this article was checked against current official source material from the Department of Health and Social Care and current sector guidance on 22 July 2026. The first pay rate and detailed agreement terms have not yet been negotiated. Check the latest regulations and official guidance before making employment, payroll, contractual or financial changes. This article provides general provider guidance and does not replace legal, HR, tax, accountancy or regulatory advice for a specific organisation.

    Frequently Asked Questions

    What is the adult social care Fair Pay Agreement?

    It is a planned negotiating system for pay and employment terms in England’s adult social care sector. An Adult Social Care Negotiating Body will bring together equal worker and employer representation. Once an agreement is negotiated and ratified, the government says it will become part of covered workers’ contracts. The detailed first agreement, including the pay rate, has not yet been decided.

    When will the first social care Fair Pay Agreement take effect?

    The government intends the first agreement to take effect from April 2028. Its current timetable anticipates regulations in 2026, establishment and appointments during 2026 to 2027, and the first negotiation period beginning around April 2027. Providers should monitor official updates because implementation details may change as regulations, appointments and guidance are completed.

    Which adult social care workers are expected to be covered?

    The current design covers the paid adult social care workforce within the statutory scope in England. Workers already covered by Agenda for Change, the NHS Pay Review Body or National Joint Council arrangements are excluded. Unpaid carers, self-employed workers and informal care arrangements are outside current coverage. Providers should test mixed or unusual roles against the final regulations rather than relying only on job titles.

    Has the Fair Pay Agreement pay rate been decided?

    No. The first rate and detailed employment terms will be negotiated by the future Adult Social Care Negotiating Body. The £500 million first-year funding envelope is not an announced wage rate and should not be converted into one. Providers can model variable scenarios for planning, but every scenario should be clearly labelled as an assumption rather than government policy.

    What should care providers do now?

    Build a controlled readiness plan. Map potentially covered roles, reconcile payroll and working-time evidence, model variable cost scenarios, identify contract change routes, prepare commissioner evidence and assign board-level ownership. Keep current minimum wage compliance separate from future Fair Pay Agreement preparation, and update the plan when regulations or official guidance clarify the unresolved terms.

    For a concise official overview of scope and common questions, review the Skills for Care Fair Pay Agreement FAQs.

  • ASC-WDS 2026: A Practical Guide to Workforce Records and Training Funding for Care Providers

    ASC-WDS 2026: A Practical Guide to Workforce Records and Training Funding for Care Providers

    ASC-WDS is the free Adult Social Care Workforce Data Set run by Skills for Care for employers in England. It can help you manage workplace, staff, qualification and training records. For the 2026 to 2027 Adult Social Care Learning and Development Support Scheme, an up-to-date ASC-WDS account is also a condition of claiming eligible training costs.

    The distinction matters. ASC-WDS is not a universal legal requirement for every independent care provider. It becomes a specific funding condition when an employer wants reimbursement through the current scheme. Treat the account as a live workforce record, not a form you complete once and forget.

    What is ASC-WDS?

    The Adult Social Care Workforce Data Set, usually shortened to ASC-WDS, is an online service hosted and administered by Skills for Care. Employers enter information about their workplace and workforce. Skills for Care uses aggregated, anonymous data to build intelligence about the adult social care sector.

    Your account can hold workplace information such as service type, capacity, vacancies, starters and leavers. Staff records can include employment details, contracted hours, pay, sickness, qualifications and Care Certificate completion. Once staff records are in place, you can also use the service to monitor training and qualification records and identify gaps.

    ASC-WDS useWhat it can help you doImportant boundary
    Workforce managementMaintain workplace and staff information in one structured serviceDo not assume the account replaces your HR, payroll or compliance records
    Training oversightRecord courses, qualifications and renewal datesA recorded course does not by itself prove workplace competence
    Sector intelligenceContribute anonymised data used for workforce analysisCheck your privacy information and internal data responsibilities
    Training fundingMeet one of the conditions for an eligible 2026 to 2027 claimFunding remains subject to all scheme conditions and available funds
    ASC-WDS supports several workforce tasks, but each use has a separate evidence boundary.

    Is ASC-WDS mandatory for care providers?

    No general rule makes ASC-WDS mandatory for every independent care provider. The current funding rules are narrower and more precise. If an adult social care employer in England wants to claim through the 2026 to 2027 Learning and Development Support Scheme, the employer must have an up-to-date ASC-WDS account and meet the service’s minimum data requirements before submitting the claim.

    For claims other than Oliver McGowan Mandatory Training on Learning Disability and Autism, an employer does not need to be registered with the Care Quality Commission (CQC), but must employ eligible non-regulated adult social care staff in England. Oliver’s Training has separate eligibility conditions. Always check the latest government employer guide before booking or paying for learning.

    The 2026 to 2027 funding rules at a glance

    The current grant determination applies to eligible courses and qualifications paid for between 1 April 2026 and 31 March 2027. It supports evidenced costs for eligible non-regulated care staff, including deputy managers, CQC-registered managers and agency staff. Regulated professionals are generally outside the scheme, except for the separate Oliver’s Training provision described in the rules.

    CheckCurrent 2026 to 2027 positionProvider action
    AccountASC-WDS must be up to date and meet minimum data requirementsVerify status before submitting a claim
    Payment windowEligible costs must be paid between 1 April 2026 and 31 March 2027Keep invoices and proof of payment linked to the staff member and course
    Course claimsSubmit after completion, normally within three months of completionSet a claim deadline when the course finishes
    Qualification claimsA combined 60% start claim and 40% completion claim can applyTrack both evidence points and both claim windows
    AvailabilityReimbursement is subject to remaining scheme funds and all conditionsDo not treat expected reimbursement as guaranteed income
    Use the live government guidance for the controlling rules. This table is a provider action summary, not a substitute for the scheme documents.

    Build an ASC-WDS record that is ready for a funding claim

    A strong account has three layers: an accurate workplace profile, complete staff records and a controlled maintenance routine. The funding rules require employers to meet the minimum data requirements and refresh the account annually. If a parent organisation claims for subsidiaries, the relevant workplace and staff records must be up to date for every organisation included in the claim.

    ASC-WDS workforce records workspace with an anonymised staff register, training matrix and renewal calendar
    Build the workplace, staff and training records together so the funding evidence can be traced to the right organisation and worker.

    1. Confirm the workplace record

    • Match the legal employer and workplace details to the entity making the claim.
    • Check the CQC location ID where the service is registered.
    • Confirm service type, capacity and workforce totals.
    • Map every subsidiary or workplace that will be included in a group claim.

    2. Reconcile staff records

    Compare ASC-WDS against your current employee list. Add starters, close or update leaver records, and check that roles, employment status and contracted details remain accurate. Do not upload information merely because a field exists. Use the data definitions and apply your organisation’s privacy and access controls.

    3. Connect training to the correct worker

    Record the relevant course or qualification against the right staff member, but keep the supporting evidence in your controlled training or finance system. Your evidence pack may need employment confirmation, National Insurance information for identity verification, proof that the learning is eligible, course start or completion evidence, invoices and proof of payment.

    Use the five-gate claim method

    Before finance treats a reimbursement as claimable, move it through five gates. This method keeps the workforce account, course decision and evidence trail aligned.

    Five-stage ASC-WDS funding evidence journey from workplace profile to reimbursement tracking
    The five gates are workplace, worker, eligibility, evidence and claim control.
    GateDecision questionMinimum evidenceOwner
    1. WorkplaceIs the claiming employer eligible and correctly recorded?ASC-WDS workplace status and legal entity checkRegistered Manager or workforce lead
    2. WorkerIs this worker and role within the current scheme?Employment and role evidenceHR lead
    3. LearningWas the course or qualification eligible at the relevant booking or payment point?Saved copy or link to the applicable eligibility guidanceLearning lead
    4. EvidenceCan every claimed cost and completion point be proved?Invoice, payment evidence and course or qualification recordFinance lead
    5. ClaimIs the claim within the correct deadline, cap and available-funds condition?Claim log, deadline and approval recordAuthorised claimant
    Assign an owner to each gate. A shared responsibility without a named owner is easy to miss.

    Manage the two clocks

    ASC-WDS and the funding scheme run on different clocks. Your account needs an annual refresh to retain up-to-date status. Individual course and qualification claims have their own evidence and submission deadlines. A provider can therefore have a recently refreshed account and still miss a claim window, or have complete course evidence but fail the account condition.

    ClockTriggerControl
    ASC-WDS maintenanceAnnual account refresh, plus real workforce changesMonthly data reconciliation and an annual status check
    Funding claimCourse completion, qualification start or qualification completionDeadline entered when the evidence event occurs
    Guidance freshnessBooking, payment and claim preparationSave the applicable guidance version and recheck the live page

    Common ASC-WDS and funding mistakes

    • Calling ASC-WDS a universal legal requirement. Describe the exact context. It is a current scheme condition for eligible claims, not a blanket rule for every independent provider.
    • Updating only the workplace record. Minimum data requirements can depend on staff records as well as the workplace profile.
    • Leaving subsidiaries out of the reconciliation. Group claims require the relevant records for each organisation included.
    • Assuming every course is funded. Check the current eligible learning list at the relevant booking or payment point.
    • Using ASC-WDS as the only evidence store. Retain invoices, payment proof, completion evidence and internal approvals in controlled systems.
    • Waiting until the claim deadline. Limited scheme funds mean reimbursement cannot be guaranteed. Prepare the evidence promptly.

    For the separate competence and inspection evidence layer, read our 2026 guide to mandatory training for care workers. It explains why a certificate or data entry is not the same as proving that a worker can apply learning safely in practice.

    A monthly ASC-WDS governance checklist

    • Reconcile starters, leavers and role changes against HR records.
    • Review workplace and subsidiary records included in planned claims.
    • Check training and qualification entries against the training matrix.
    • Confirm that each planned claim still meets the live eligibility rules.
    • Test that invoices, payment evidence and completion records are retrievable.
    • Review approaching account and claim deadlines.
    • Record the review date, exceptions, actions and named owner.

    How Care Sync Experts can help

    Care Sync Experts can help you connect workforce data, training records, competence evidence and management oversight into one practical governance system. Our Compliance Management support can review record ownership, evidence controls, training gaps and audit routines alongside your wider regulatory responsibilities.

    If you want an independent review of your ASC-WDS readiness, training evidence or claim-control process, book a consultation with Care Sync Experts.

    Frequently asked questions

    What does ASC-WDS stand for?

    ASC-WDS stands for Adult Social Care Workforce Data Set. It is the free workforce data service hosted and administered by Skills for Care for adult social care employers in England.

    Is ASC-WDS the same as NHS Capacity Tracker?

    No. ASC-WDS is Skills for Care’s workforce data service. NHS Capacity Tracker is a separate government service used for operational capacity and related provider information. Keep separate owners, deadlines and evidence for the two systems. Our NHS Capacity Tracker 2026 guide explains that reporting route.

    Do I need ASC-WDS to claim training funding in 2026 to 2027?

    Yes, if you want to claim through the 2026 to 2027 Adult Social Care Learning and Development Support Scheme. The employer must have an up-to-date ASC-WDS account and meet the minimum data requirements before submitting a claim.

    How often should an ASC-WDS account be updated?

    The 2026 to 2027 grant determination says employers must update the account annually to retain up-to-date status. A safer operational approach is to reconcile material workforce changes throughout the year and complete a formal annual refresh.

    Can ASC-WDS replace my training matrix?

    ASC-WDS can help you record training and qualification information, identify gaps and receive renewal notifications. You still need controls that show role-specific requirements, competence checks, evidence ownership and the records your organisation relies on for governance.

    Is reimbursement guaranteed once my ASC-WDS account is up to date?

    No. An up-to-date account is one condition. The course or qualification, worker, payment, evidence and submission timing must also meet the scheme rules. Reimbursement is also subject to sufficient funds remaining.

    Official source check completed 22 July 2026. The funding guidance can change. Recheck the 2026 to 2027 grant determination, the current employer guidance, the Skills for Care ASC-WDS overview and the getting started guidance before committing to learning or submitting a claim.

  • Data Security and Protection Toolkit for Care Providers: A Practical DSPT Guide for 2026

    Data Security and Protection Toolkit for Care Providers: A Practical DSPT Guide for 2026

    DSPT, the Data Security and Protection Toolkit, is the official self-assessment tool for data protection and cyber security in adult social care in England. Care providers with access to personal information held in NHS systems must use it. Providers working under an NHS Standard Contract also have a contractual requirement to complete it each year. Other adult social care services are strongly recommended to complete it and aim for Standards Met.

    The 2025 to 2026 deadline was 30 June 2026. If your service missed it, keep going. Digital Care Hub’s post-deadline guidance says the priority is to complete the work, publish the assessment and then make sure the commitments are reflected in daily practice. This guide gives you a practical recovery plan, an evidence matrix and a twelve-month maintenance cycle.

    Data Security and Protection Toolkit work is not limited to software. The Data Security and Protection Toolkit covers the information you hold about people who use services, staff, visitors, commissioners and partners. That includes paper records, conversations, mobile devices, emails, care systems and information sharing.

    Key Takeaways

    • Check whether toolkit completion is mandatory for your service or strongly recommended. Do not assume the same position applies to every CQC provider.
    • If the 30 June 2026 deadline has passed, finish the assessment and publish as soon as your evidence is accurate.
    • Gather evidence before answering. Policies alone do not prove that controls work in practice.
    • Aim for Standards Met. If you are using an action-plan route, record ownership, dates and evidence for every gap.
    • Treat publication as the start of an annual control cycle, not a once-a-year form-filling exercise.

    What Is the Data Security and Protection Toolkit?

    The NHS Data Security and Protection Toolkit, usually shortened to DSPT, is a free online self-assessment. It helps health and care organisations measure how they manage data security and information governance against the National Data Guardian’s 10 data security standards.

    The current NHS Adult Social Care Standards Directory records DSPT version 8 as active. It applies to organisations with access to personal information held in NHS systems, organisations supporting NHS bodies, social care providers delivering through the NHS Standard Contract and other listed organisations.

    For adult social care, Digital Care Hub explains that the Data Security and Protection Toolkit covers policies, procedures and real operating processes. It includes paper records, verbal disclosures, digital systems, cyber security and the duty to share information safely for a person’s care. That wider scope matters. A provider cannot complete strong toolkit evidence by asking an IT supplier to answer every question.

    What does Standards Met mean?

    Standards Met is the level adult social care providers should aim to reach. It means your published assessment contains the mandatory evidence required for that level. It does not certify that a service will never experience a data breach, and it does not replace ongoing risk management.

    Reaching Standards Met can support access to shared systems and helps provide assurance to NHS partners, commissioners, people using services and staff. Digital Care Hub also explains that providers need at least Approaching Standards for NHSmail access. Check the current access rules before relying on the toolkit for a particular system.

    Who Needs to Complete the Data Security and Protection Toolkit?

    Use the following distinction carefully.

    Your positionCurrent positionPractical response
    Your organisation has access to personal information held in NHS systemsNHS England says you must use the toolkitConfirm your organisation code, scope and annual publication status
    Your care service is funded through an NHS Standard ContractCompletion is a contractual requirementCheck the contract, commissioner requirements and target publication level
    Your adult social care service does not fall into either group aboveDigital Care Hub says all adult social care services in England are strongly recommended to complete itUse the toolkit as a recognised assurance framework and aim for Standards Met
    A council or Integrated Care Board contract specifies the toolkitYour contract may create a specific obligationCheck the exact wording, deadline, level and reporting route

    Do not describe DSPT as legally mandatory for every CQC-registered provider. That wording is too broad. Equally, do not dismiss it as optional administration. CQC’s Chief Inspector of Adult Social Care publicly recommended in July 2026 that all care providers use DSPT to improve how they manage personal data.

    The distinction is operationally important. A provider funded by the NHS may have a clear contractual requirement. Another provider may be responding to commissioner expectations, NHSmail access conditions, CQC evidence needs or its own governance priorities. Record which basis applies to your service.

    Missed the 30 June 2026 Data Security and Protection Toolkit Deadline?

    The annual deadline for the 2025 to 2026 toolkit was 30 June 2026. Missing the date does not make unfinished work disappear. Digital Care Hub’s current message is to keep going. Complete the remaining evidence, correct weak answers and publish when the assessment is accurate.

    Start your Data Security and Protection Toolkit recovery with a short meeting. Confirm the registered organisation, service scope, current assessment status, outstanding questions, evidence owners and target publication date. If a commissioner or NHS partner requires DSPT, tell the relevant contract lead what you are doing and follow the contract’s reporting route.

    Do not rush unsupported answers simply to obtain a publication status. The published assessment should match your real controls. If an answer depends on a policy, training record, supplier assurance, backup test or incident procedure that does not exist, treat that as an action rather than writing as if it is already in place.

    Data Security and Protection Toolkit: 7 Practical Steps

    1. Lock the organisation and assessment scope

    Confirm the correct legal organisation, Organisation Data Service code, locations and services. Decide which people, systems, devices, suppliers and records are inside the assessment. A weak scope can produce confident answers about only part of the organisation.

    2. Assign accountable owners

    Name one DSPT lead and give each evidence area an owner. The registered manager may co-ordinate the work, but information governance, HR, operations and IT support may each hold essential evidence. Record who approves the final assessment.

    3. Build evidence before answering

    Create an evidence register with five fields: question or control, source record, owner, last review date and verification status. This turns the toolkit into a controlled assurance exercise. It also stops the team relying on memory or copying last year’s answer.

    DSPT evidence workspace with policy, training, supplier and continuity records
    Build one evidence register that connects each DSPT answer to a current record, named owner, review date and verification check.

    4. Test whether each control works

    Do not stop at document existence. Check whether staff understand their responsibilities, access is removed when people leave, backups can be restored, mobile devices are controlled, suppliers are reviewed and incident procedures work under pressure. Record the test and the result.

    5. Answer with precise, current evidence

    Use the live toolkit and current official question guidance. Answer for your service as it operates now. Where a control is incomplete, use the permitted action-plan route only if it genuinely applies and describe the gap, action, owner and target date accurately.

    6. Run an independent challenge

    Ask a leader who did not write the answers to test them against source records. Challenge vague phrases such as ‘staff are trained’ or ‘backups are completed’. A reviewer should be able to find the training evidence, completion status, backup frequency and latest restore test.

    7. Publish, archive and schedule the next review

    Publish only after the organisation and evidence have been checked. Save the publication record, evidence register, review notes and action plan. Then add quarterly checks and an annual republish date to the governance calendar.

    Data Security and Protection Toolkit Evidence Matrix for Adult Social Care

    Digital Care Hub groups the social care questions across staffing and roles, policies and procedures, data security, and IT systems and devices. The Data Security and Protection Toolkit matrix below adds a practical verification layer.

    Evidence areaRecords to gatherControl testWarning sign
    Roles and trainingRole descriptions, induction, refresher training, competency checks and leaver recordsSample whether staff can explain secure handling and escalationTraining is recorded but overdue or not linked to role
    Policies and privacy informationData protection policy, privacy notices, retention schedule and information-sharing procedureCompare documents with actual records, systems and sharing routesGeneric policy wording does not match the service
    Access and devicesUser lists, permissions, device register, mobile controls and software update recordsSample joiners, movers and leavers; check unsupported softwareDormant accounts or shared credentials remain active
    SuppliersContracts, data-processing terms, assurance evidence and review recordsTrace which suppliers handle personal data and how risks are monitoredNo owner knows what data a supplier can access
    Backups and continuityBackup logs, restore tests, business continuity plan and downtime recordsRun a controlled restore or downtime exerciseBackups exist but have never been restored
    Incidents and breachesIncident log, response procedure, investigation records and learning actionsTabletop test who acts, who decides and how evidence is retainedStaff know to report but do not know the route
    Records lifecycleInformation asset register, retention rules, disposal evidence and archive controlsSample records from creation to secure disposalPaper, email and exported files fall outside the register

    This matrix is a Care Sync Experts working method, not a replacement for the live toolkit. Use it to organise evidence, then answer the current DSPT questions and follow the official help text.

    How to Maintain the Data Security and Protection Toolkit Throughout the Year

    A strong Data Security and Protection Toolkit annual return is built through routine governance. Use a simple cycle.

    FrequencyMinimum reviewEvidence retained
    MonthlyJoiners and leavers, access exceptions, incidents, training gaps and device changesException log and completed actions
    QuarterlySupplier changes, information assets, policy actions, backup results and cyber alertsGovernance review record
    After a material changeNew care system, location, contract, supplier, data-sharing route or serious incidentRisk review, updated register and approved control changes
    Six to eight weeks before publicationFull evidence refresh and answer challengeCompleted evidence register and correction log
    After publicationArchive, action-plan ownership and lessons for the next cyclePublication record and dated improvement plan

    This cadence makes the toolkit useful. It also helps leaders show how data protection commitments connect with workforce management, business continuity, supplier oversight and quality governance.

    Common DSPT Mistakes to Avoid

    • claiming DSPT is mandatory for every CQC provider without checking the service’s position;
    • treating the toolkit as an IT-only task;
    • copying last year’s answers without checking changes;
    • using a policy as proof that staff follow the control;
    • forgetting paper records, verbal disclosures, mobile devices or exported files;
    • listing backups without testing whether data can be restored;
    • overlooking suppliers that can access or host personal data;
    • publishing before gaps, owners and dates are accurate;
    • failing to retain the evidence and publication record;
    • waiting until June to review twelve months of change.

    Another risk is relying on a fixed question count from an old guide. The toolkit can change between assessment years. Use the live assessment and current Digital Care Hub guidance rather than designing your evidence plan around an historic number.

    How Care Sync Experts Can Support Your Data Security and Protection Toolkit Readiness

    Care Sync Experts can help care providers connect DSPT work with wider Compliance Management. We can help organise evidence ownership, review policies and governance records, identify gaps, build an improvement tracker and prepare leaders to maintain the controls after publication.

    If your service is still establishing its wider regulatory systems, our CQC Registration Support can help align documents, responsibilities and evidence. For a focused conversation about your current DSPT position, book a consultation with Care Sync Experts.

    Evidence note: this DSPT guide was checked against current NHS England, Adult Social Care Standards Directory, Digital Care Hub and Local Government Association sources on 21 July 2026. The 2025 to 2026 deadline has passed, and question wording may change for a new assessment year. Check the live toolkit and current official guidance before making a submission or contractual decision. This guide does not replace official instructions or advice on your specific legal or contractual position.

    Frequently Asked Questions

    Is the Data Security and Protection Toolkit mandatory for all care providers?

    No. NHS England says organisations with access to personal information held in NHS systems must use it. Digital Care Hub says providers funded through an NHS Standard Contract have a contractual requirement to complete it each year. All other adult social care services in England are strongly recommended to complete it. Your council or Integrated Care Board contract may also set a specific requirement.

    What should a care provider do after missing the 30 June 2026 Data Security and Protection Toolkit deadline?

    Keep going. Confirm the assessment scope, list outstanding evidence, assign owners, correct unsupported answers and publish when the assessment is accurate. If a contract requires DSPT, follow its reporting and escalation terms. Do not invent evidence or abandon the work because the deadline has passed.

    How often should care providers complete DSPT?

    The Data Security and Protection Toolkit is an annual assessment and publication process. Digital Care Hub says providers must complete it at least once a year to keep it current. Review controls throughout the year and complete an additional review after material changes such as a new system, supplier, contract or serious data incident.

    What evidence is needed for DSPT Standards Met?

    The exact evidence depends on the live questions. Common areas include staff roles and training, policies and privacy information, access controls, devices, suppliers, backups, business continuity, incidents, retention and secure disposal. Each answer should connect to a current record and a test showing that the control works.

    Does completing DSPT ensure CQC compliance?

    No. DSPT provides recognised evidence about data protection and cyber security arrangements. It can support your wider governance evidence, but it does not determine a CQC judgement or replace the provider’s other legal, regulatory and operational responsibilities.